


- Posted
- Categories
-
- OpenPrescribing
OpenPrescribing Newsletter: Autumn 2026
Upcoming webinars, new inhaler and hospital prescribing measures, and finalised hospital medicines data through March 2026.
Upcoming webinars, new inhaler and hospital prescribing measures, and finalised hospital medicines data through March 2026.
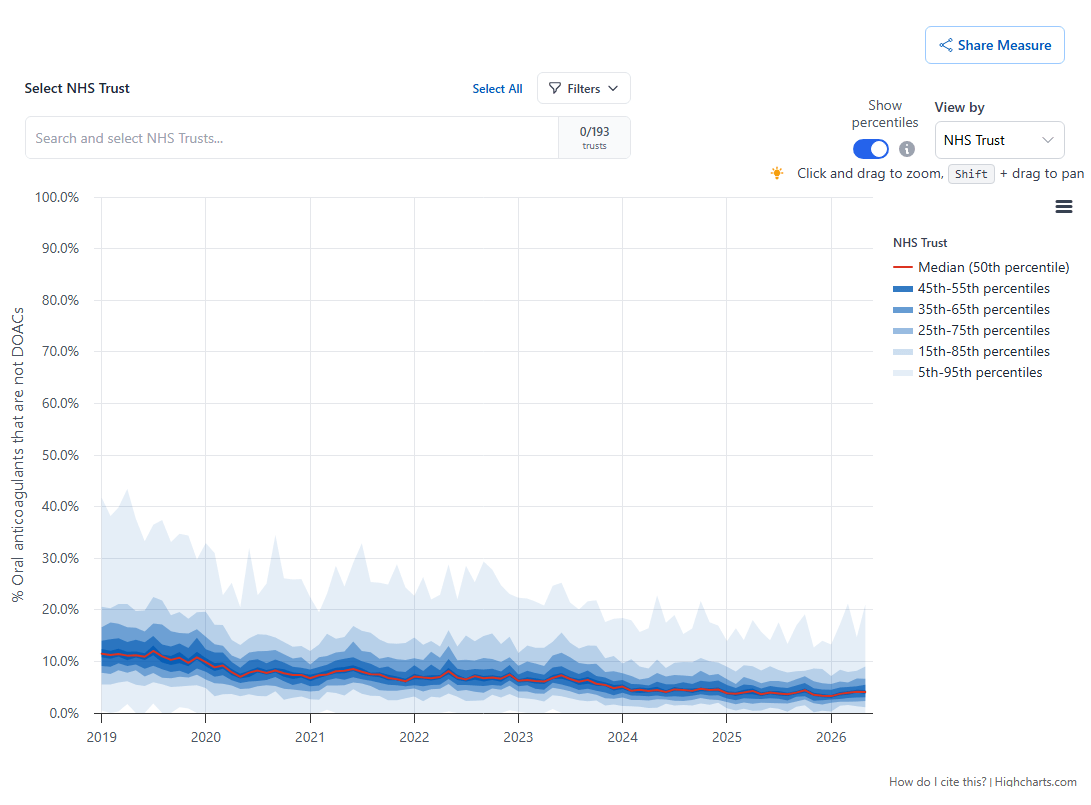
New oral anticoagulants measure has launched in OpenPrescribing Hospitals.
Najma Moallin reflects on working with real-world data, navigating uncertainty, and developing as a researcher.
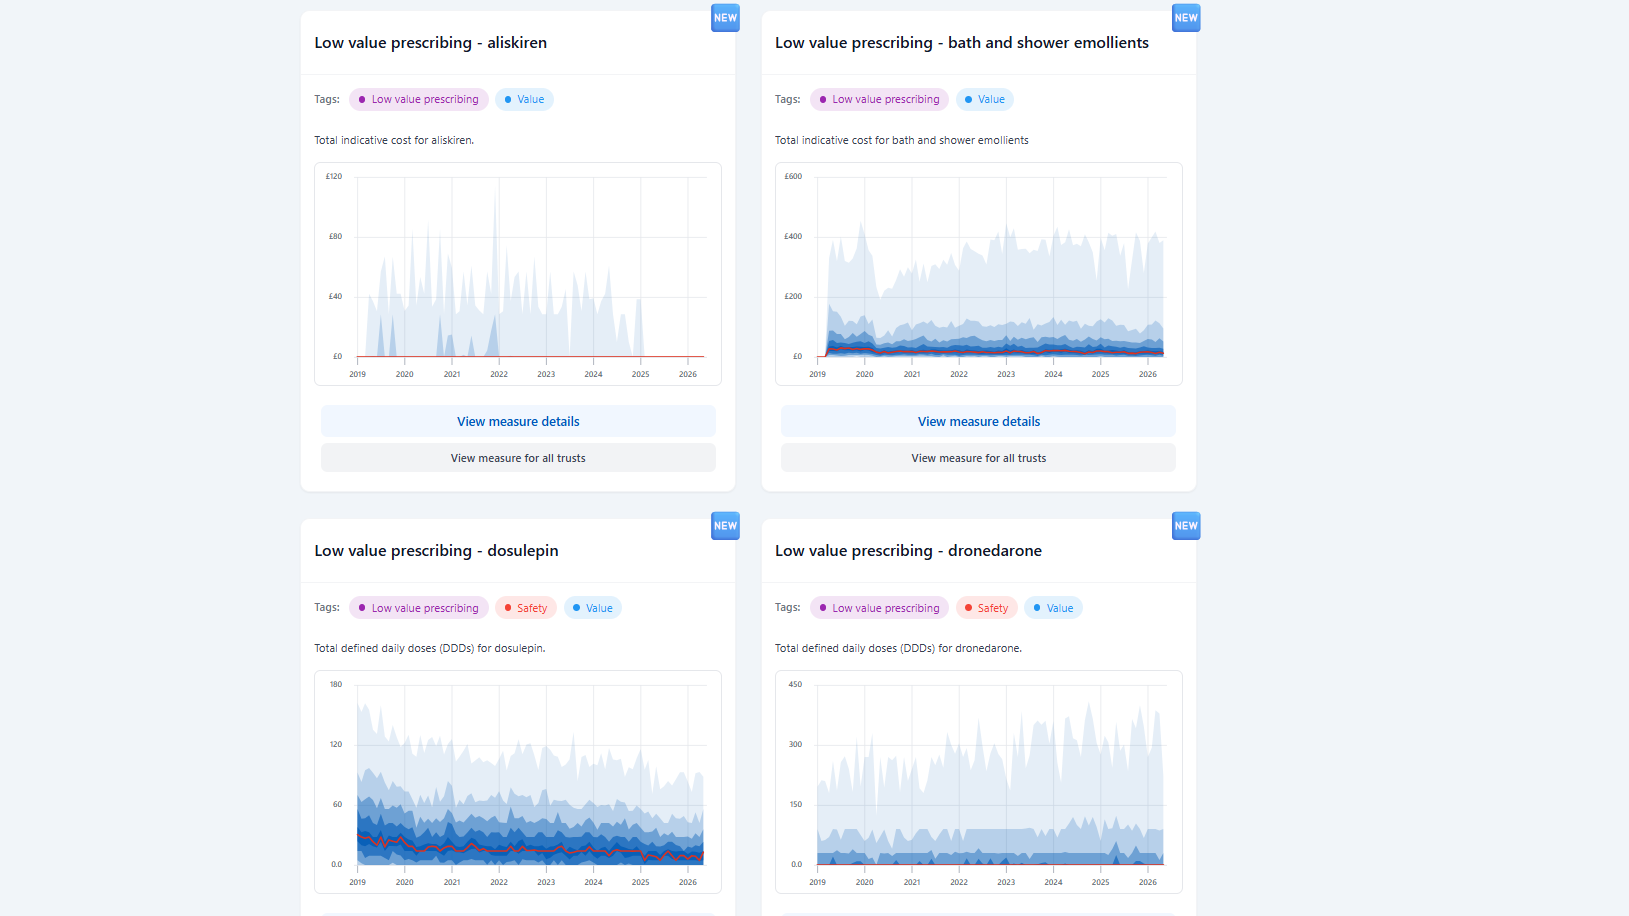
Five new low value prescribing measures have been launched.
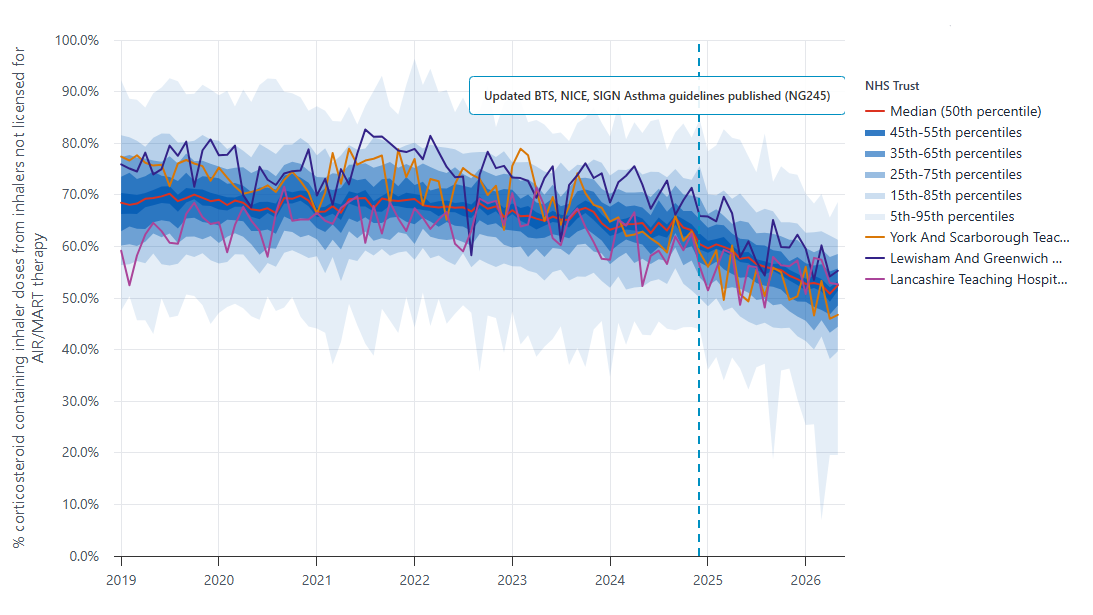
We’ve launched a new AIR/MART inhaler measure to monitor the impact of the changes introduced in the BTS/NICE/SIGN asthma guideline.
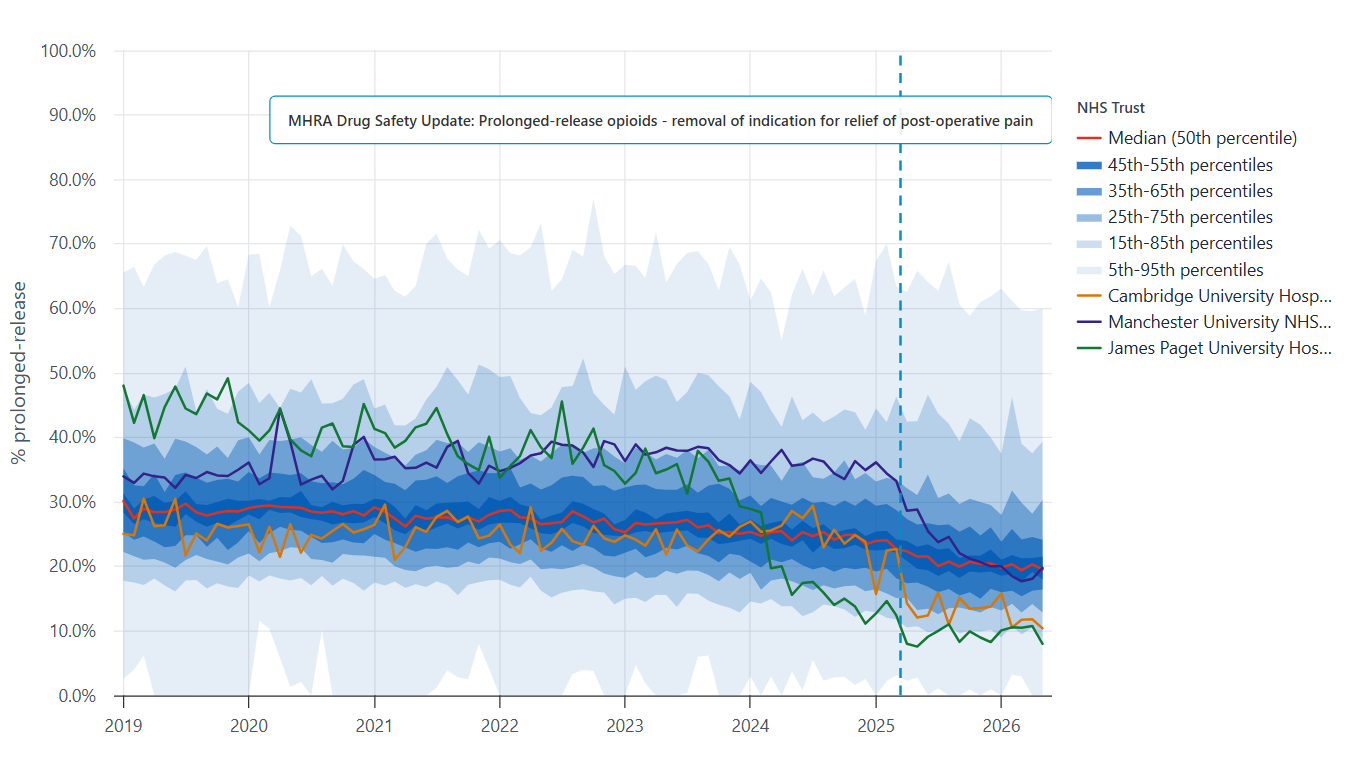
New prolonged-release morphine and oxycodone measure launched in OpenPrescribing Hospitals
Announcing the first in a series of new measures launching on OpenPrescribing Hospitals this autumn.
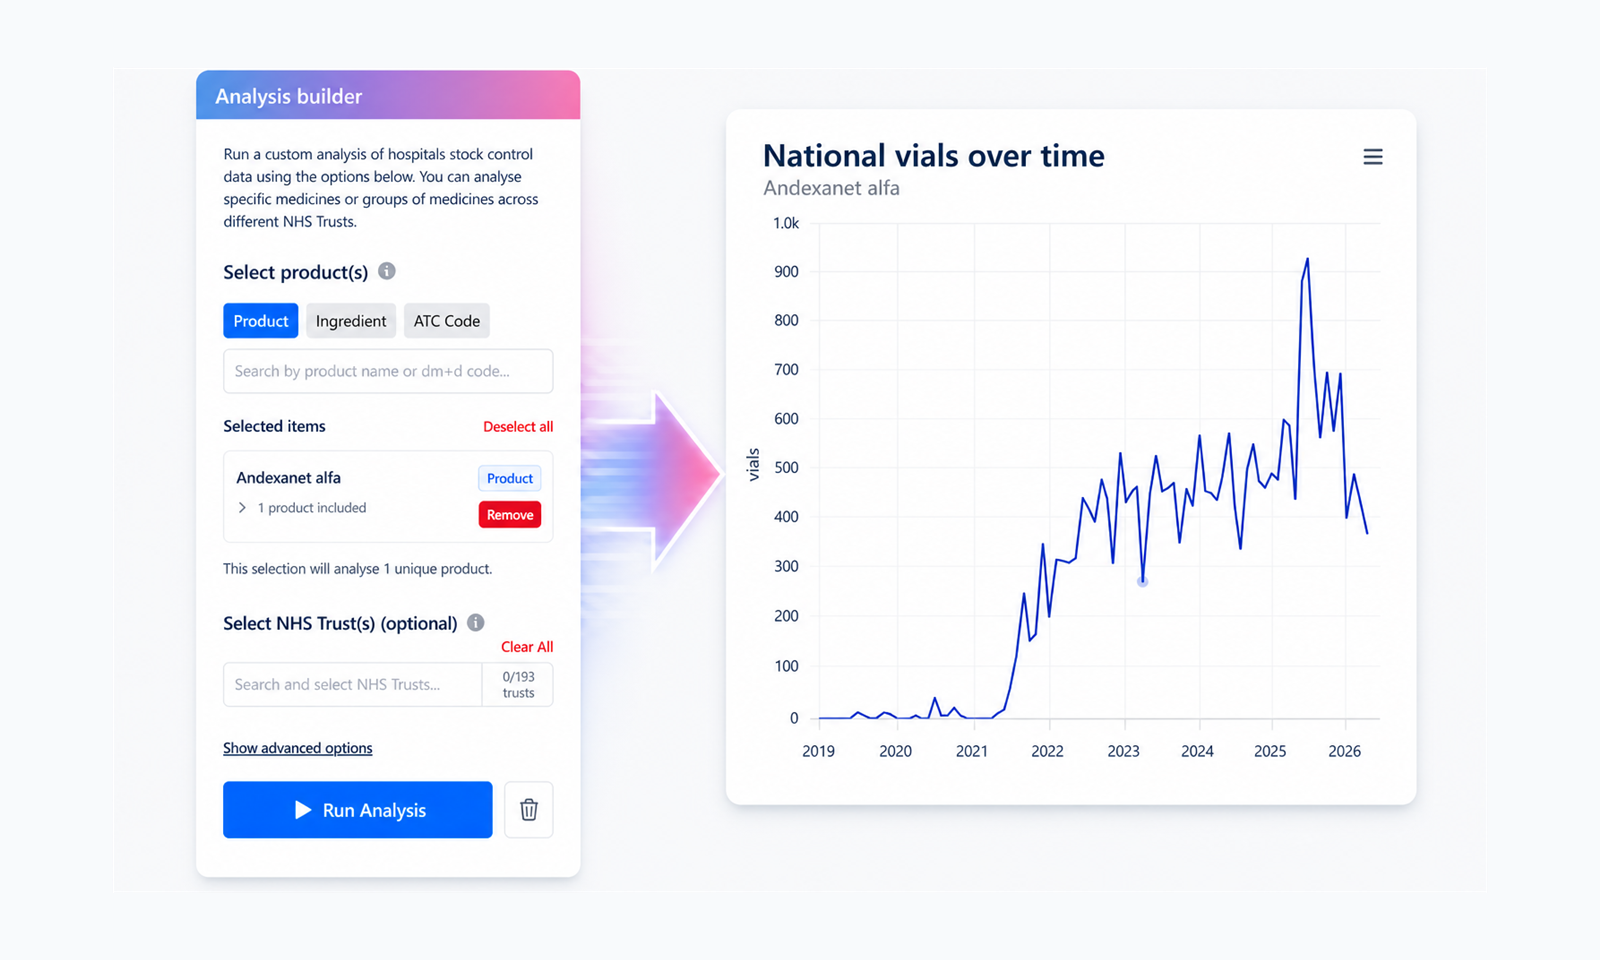
An analysis of andexanet alfa issuing in NHS trust in England using OpenPrescribing Hospitals

Clinical informatician Vicky Speed reflects on the impact of large-scale NHS GP data analysis in delivering safe and effective patient care.
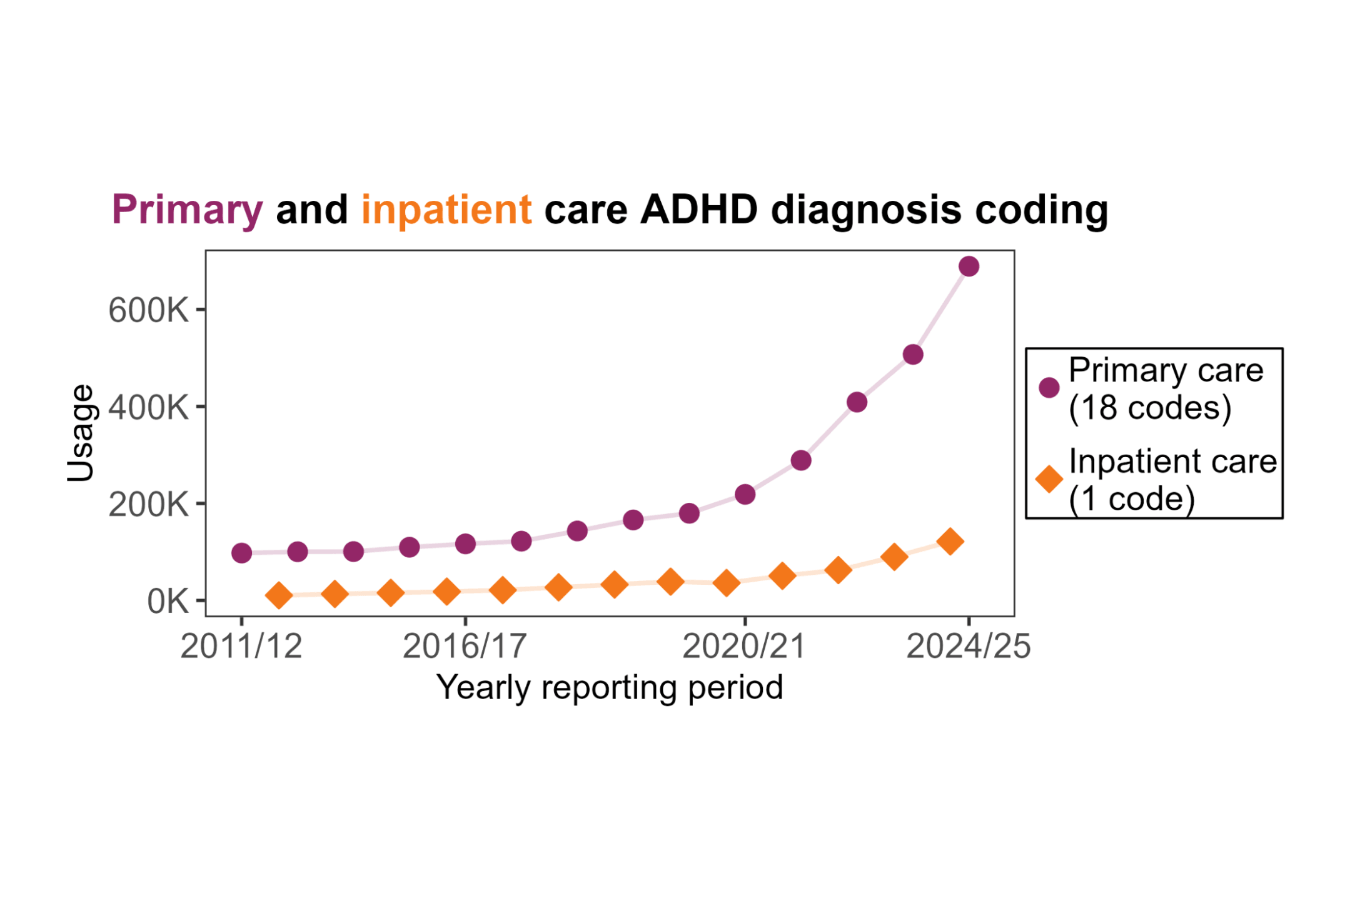
Using OpenCodeCounts and OpenPrescribing to show that ADHD diagnosis and medication coding increased in the last 10-15 years.

Covid-19 inquiry finds OpenSAFELY’s data infrastructure essential to UK’s pandemic response.

Rebuilding OpenPrescribing, a measures advisory group, hospital trust dashboards, an FP10 viewer, and new morphine and hospital measures.

Seb Bacon and Brian MacKenna showed returning graduates how healthcare data tools are developed, and explored the impact of securely analysing large-scale health data.
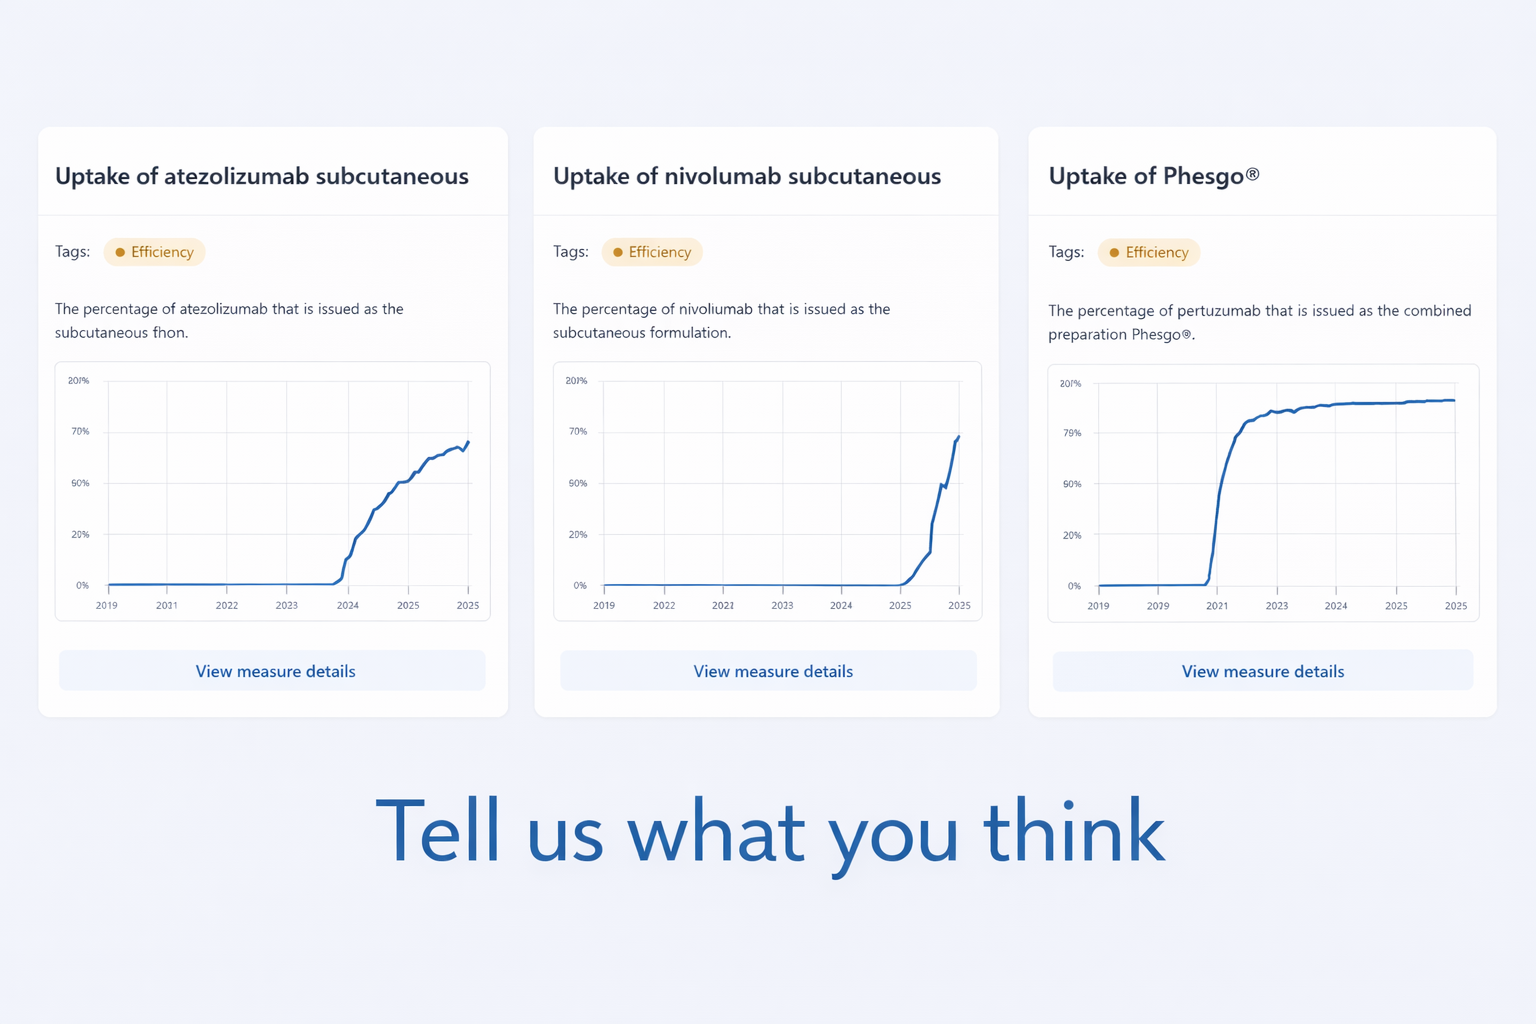
Making searching, comparing and sharing OpenPrescribing Hospitals measures easier.
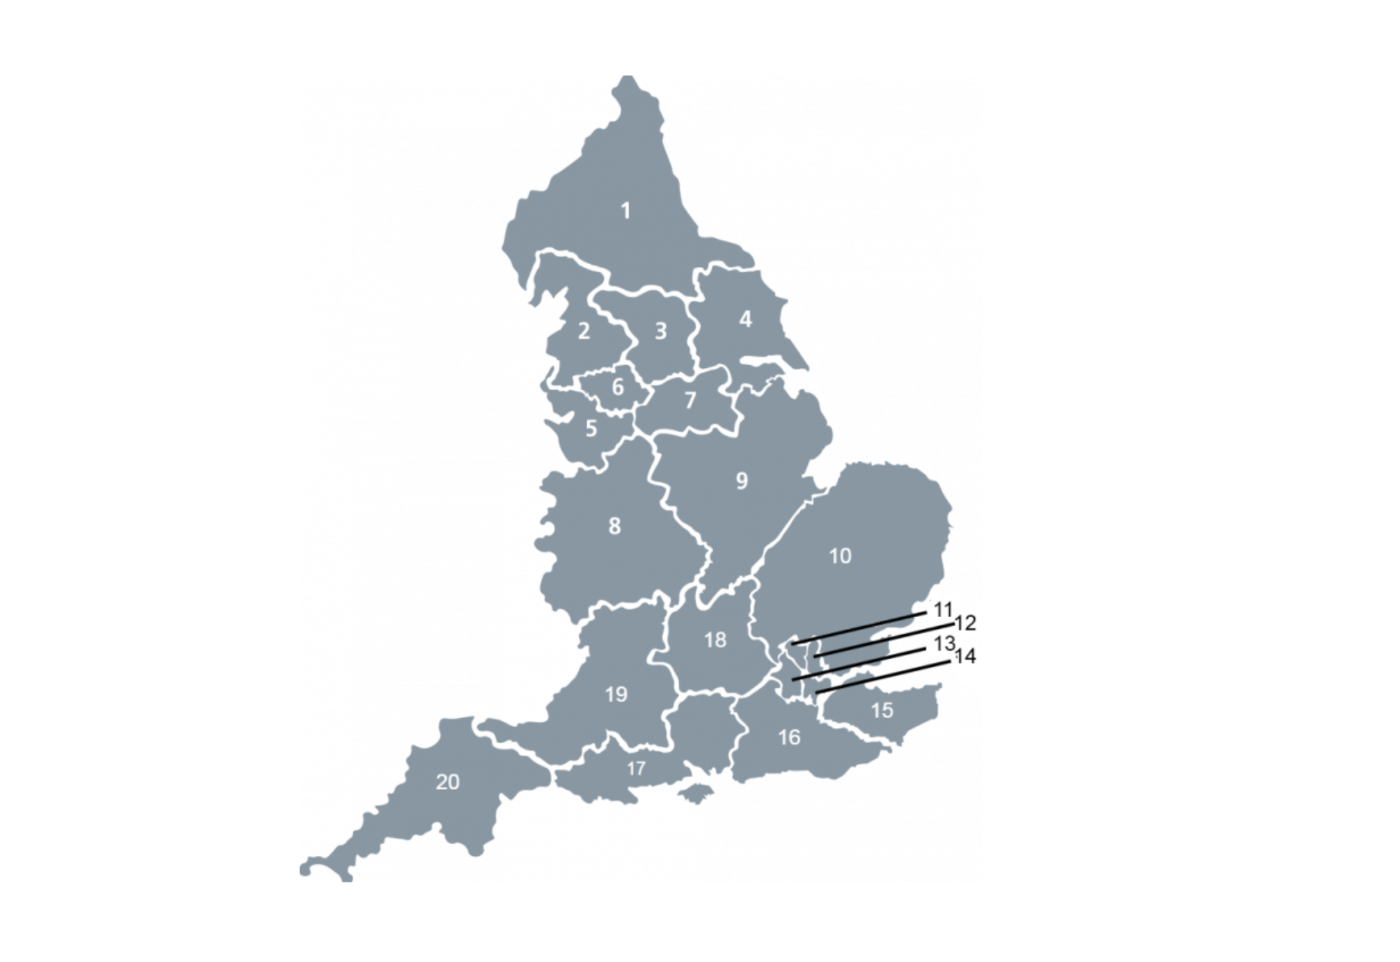
What are Cancer Alliances? How can the NHS trusts that partner with Cancer Alliances be identified?

What types of NHS trusts are there? How can they be identified?
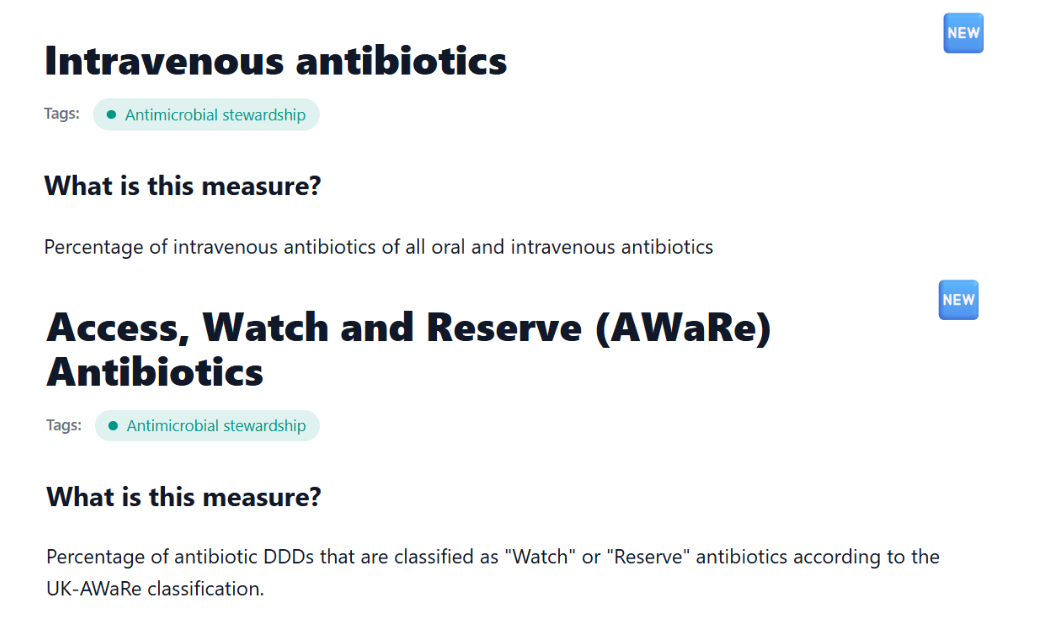
New antibiotic measures launched to support antimicrobial stewardship in hospitals.
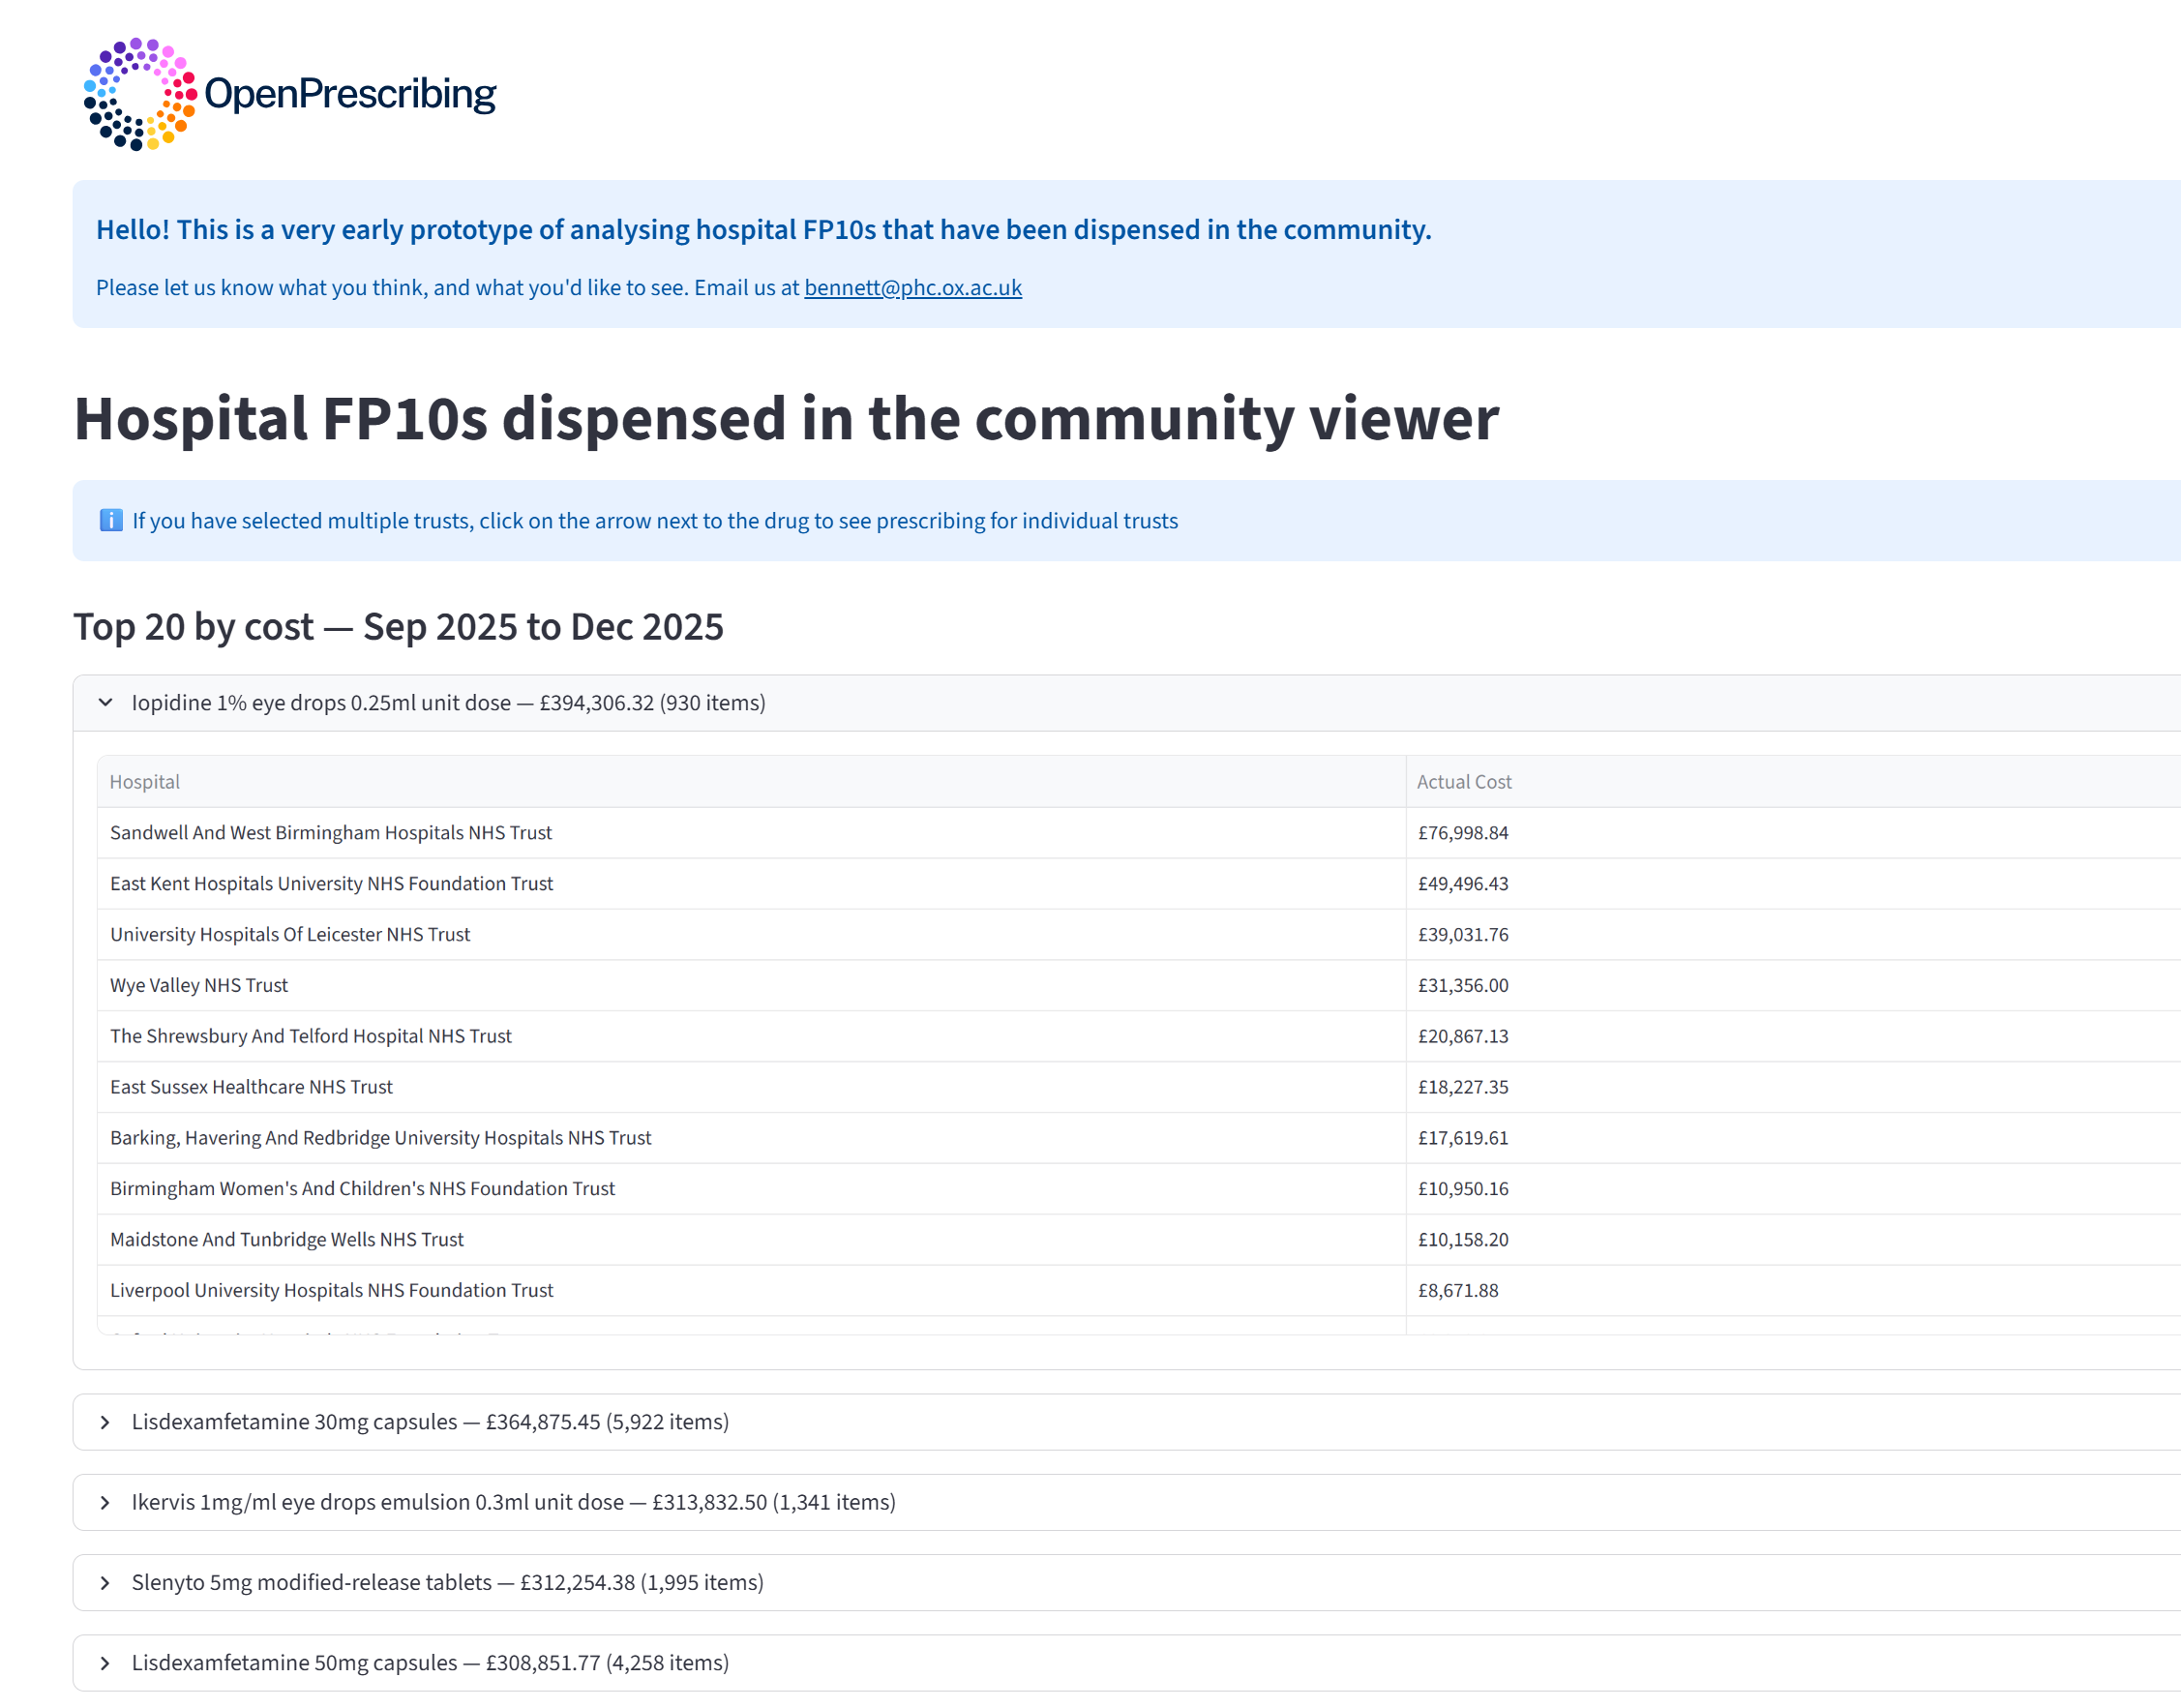
We’ve built a prototype of a tool that looks at hospital prescriptions dispensed in the community. We describe what we’ve built, how we’ve built it, and how you can help us make it better.

We share a blog written by the student winner of the Bennett Prize in OpenPrescribing

In this guest blog, Vanessa Sherwood explains how she has used OpenPrescribing to reduce oral liquid morphine prescribing.
New IV paracetamol measure launched.

We share a blog written by the academic winners of the Bennett Prize in OpenPrescribing

We share a blog written by one of our joint clinical winners..

We share a blog written by one of our joint clinical winners.

A celebration of two brilliant days bringing together 200 people from across the medicines data community, featuring keynotes, the first Bennett Prize, and OpenPrescribing’s 10th birthday.
Why it sometimes matters, and sometimes doesn’t.
We have updated the methods for blood glucose testing strips and lancets measures.

A look at how OpenPrescribing Hospitals can be used to look at warfarin and other vitamin K antagonist use in hospital trusts in England.

A look at how OpenPrescribing Hospitals can be used to look at direct oral anticoagulant use in hospital trusts in England.

A look at how OpenPrescribing Hospitals can be used to look at low molecular weight heparin anticoagulant use in hospital trusts in England.

Shareable hospital analyses, email alerts, dapagliflozin and insulin detemir measures, and OpenSAFELY’s expansion beyond COVID-19 research.

It’s now possible to easily share Measures and results of custom analyses on OpenPrescribing Hospitals. Here’s how to do it.
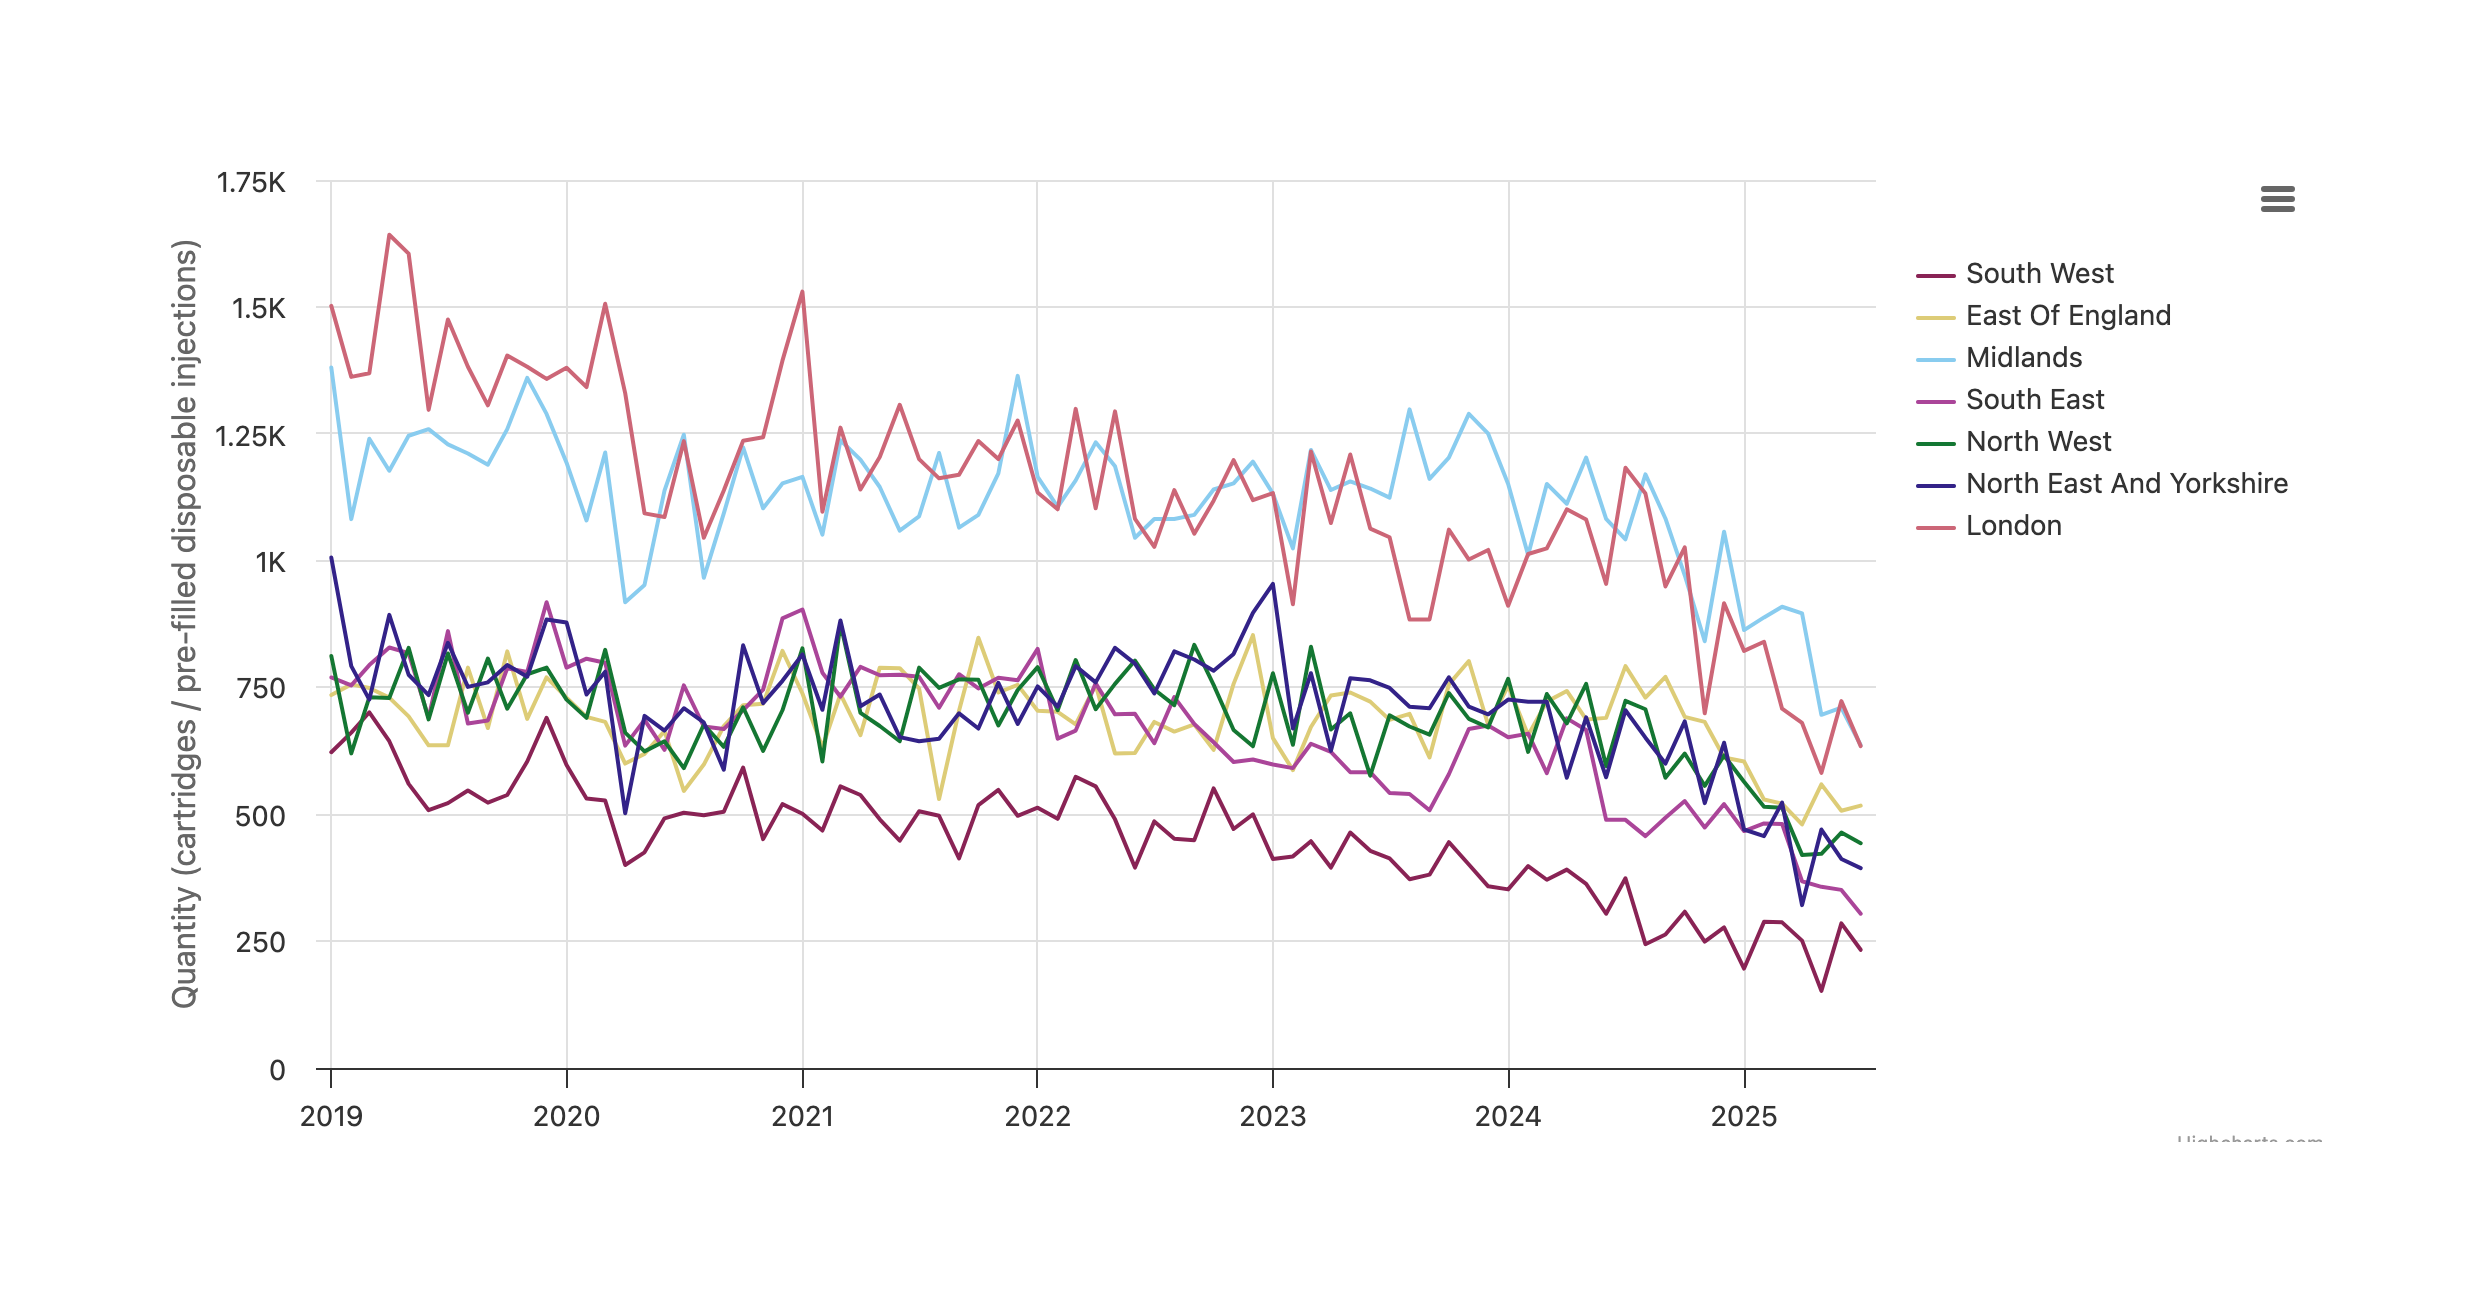
New OpenPrescribing and OpenPrescribing Hospitals measure to support work to manage the discontinuation of insulin detemir.
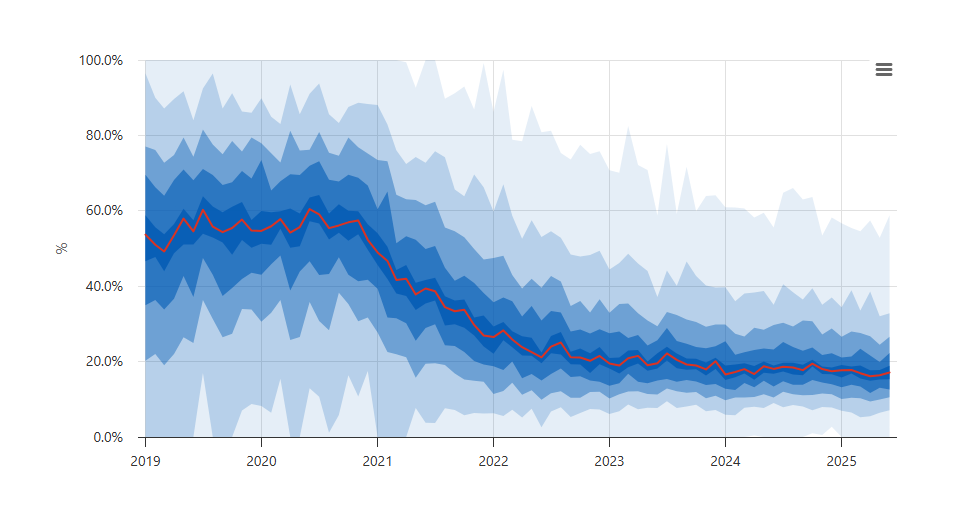
We have two new measures available now for SGLT-2 inhibitors.
Stay updated with notifications of new OpenPrescribing Hospitals features and data releases.

We’re excited to open registration and submissions of ideas for the 2025 Bennett Institute Medicines Symposium, a two-day event that brings together everyone working with NHS medicines data.

The Bennett Symposium and Prize, multiproduct hospital analyses, and new measures for low-value prescribing, dapagliflozin and AWaRe antibiotics.
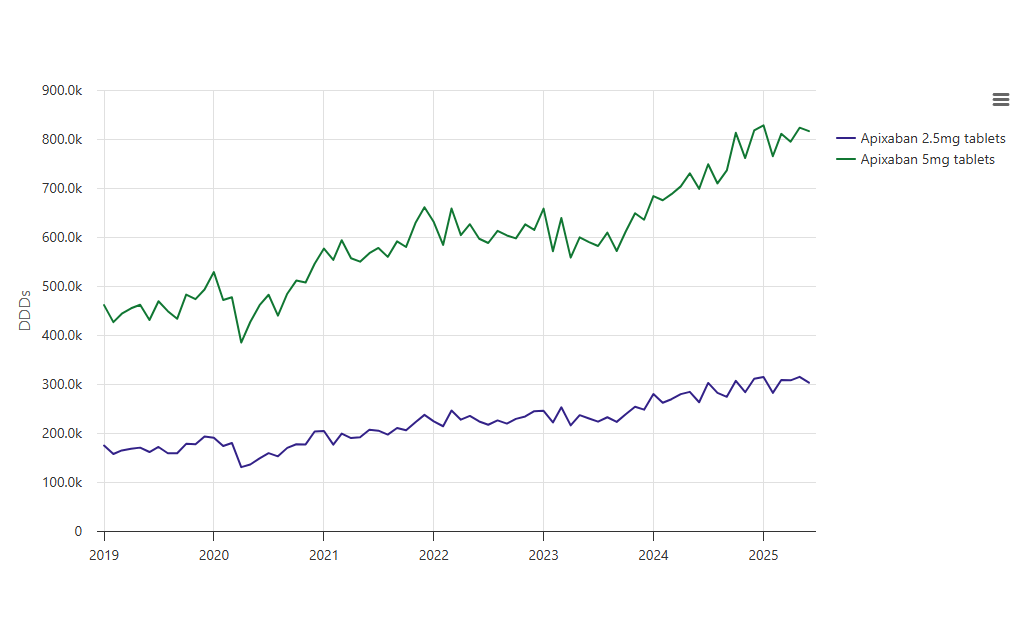
A look at how to run a multi-product analysis on OpenPrescribing Hospitals.
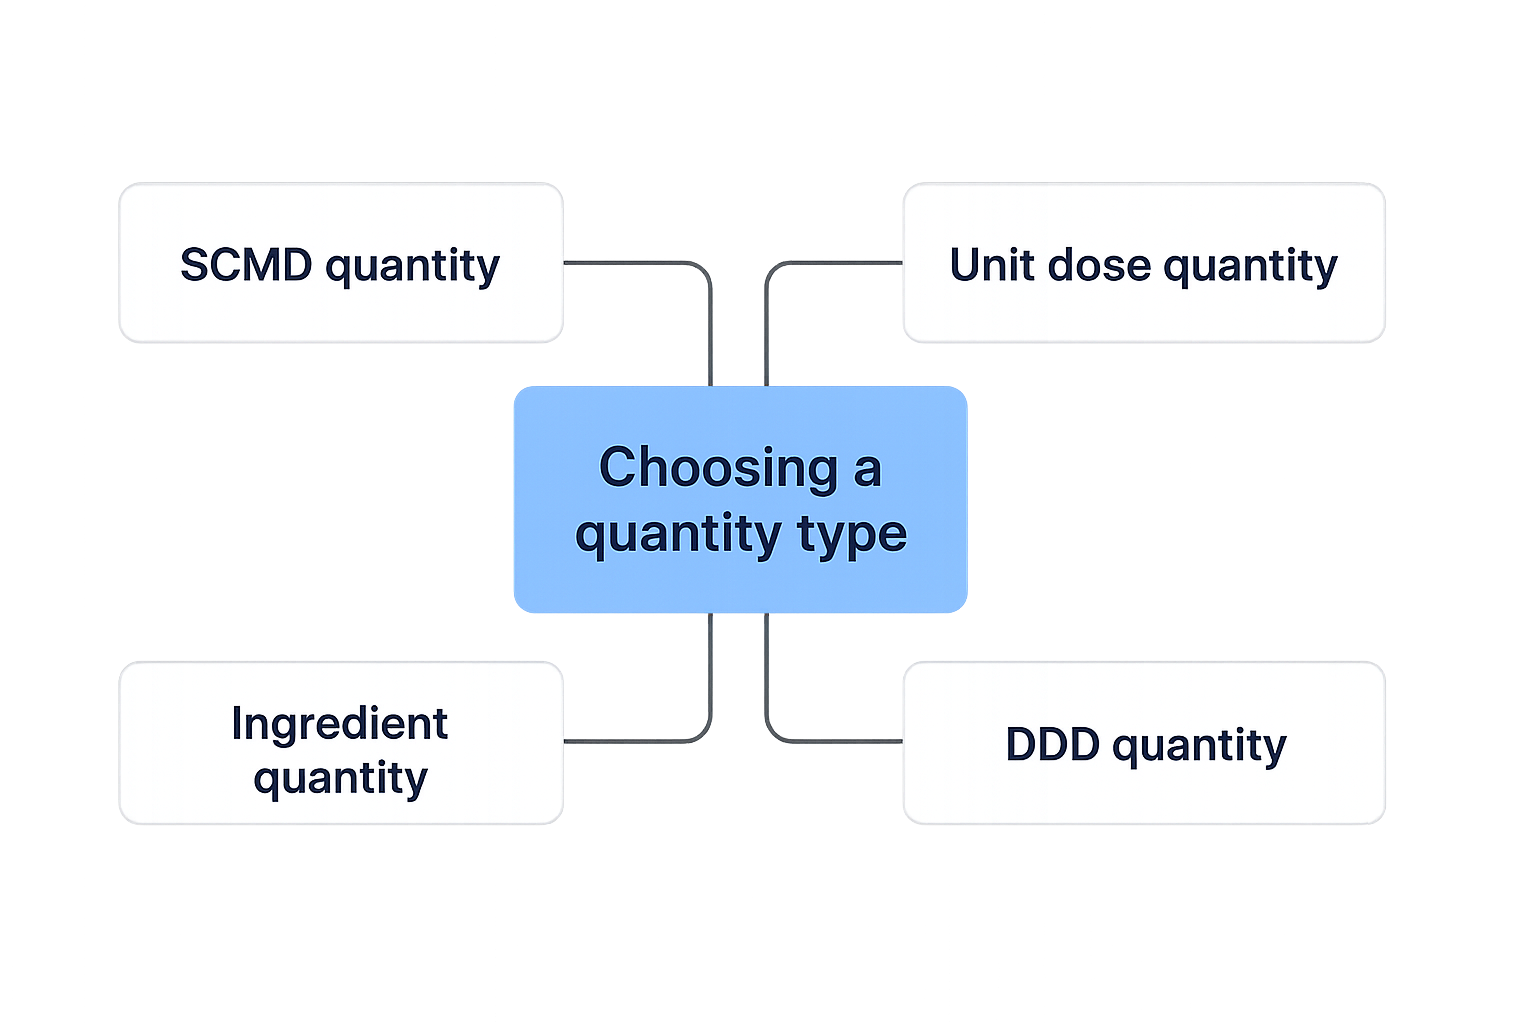
How to choose the most appropriate quantity type for custom analyses on OpenPrescribing Hospitals.
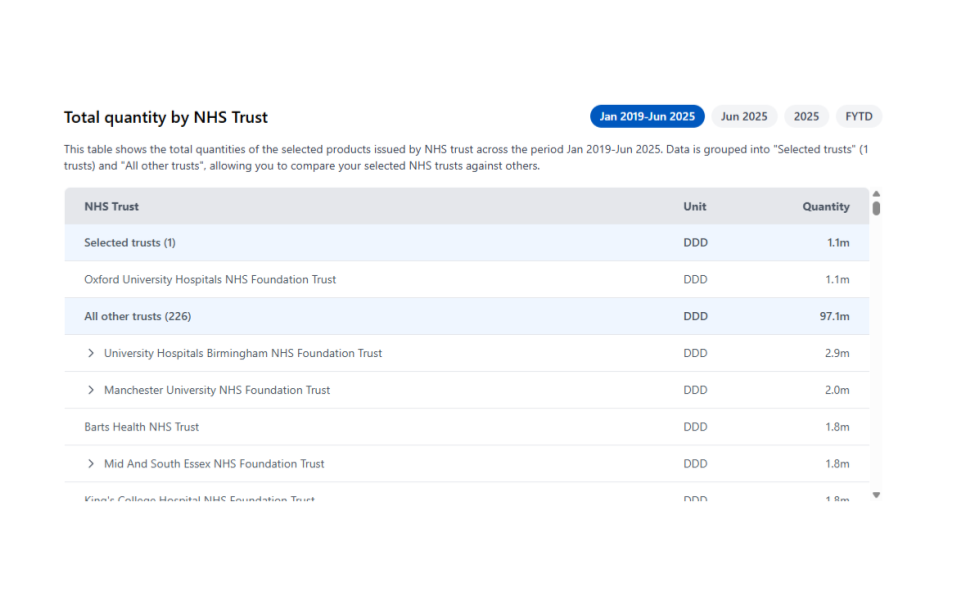
A look at how to use the summary tables produced in custom analyses on OpenPrescribing Hospitals.
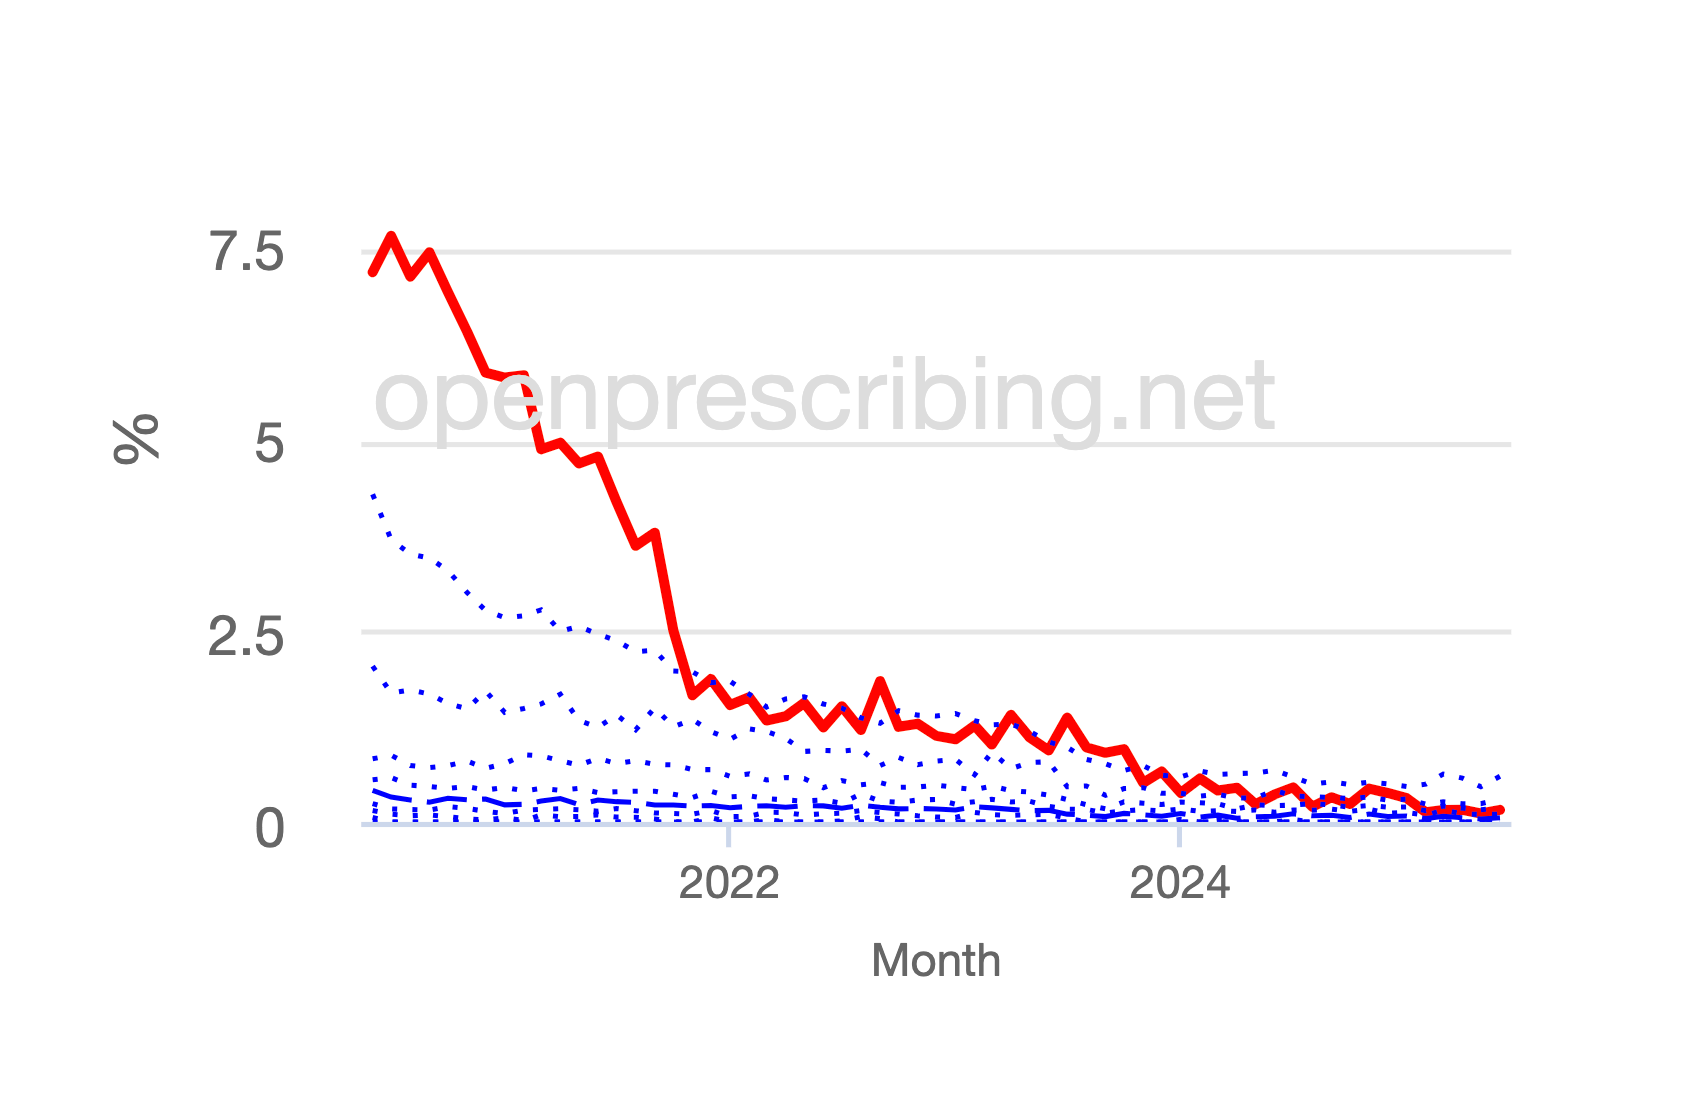
In this guest blog James Galloway a Professor of Rheumatology and an Honorary Consultant Rheumatologist in South London, at King’s College London describes how his team used OpenPrescribing to reduce unsafe methotrexate prescribing and shares his thoughts on improving quality of care may deliver most improvements for the populations health.
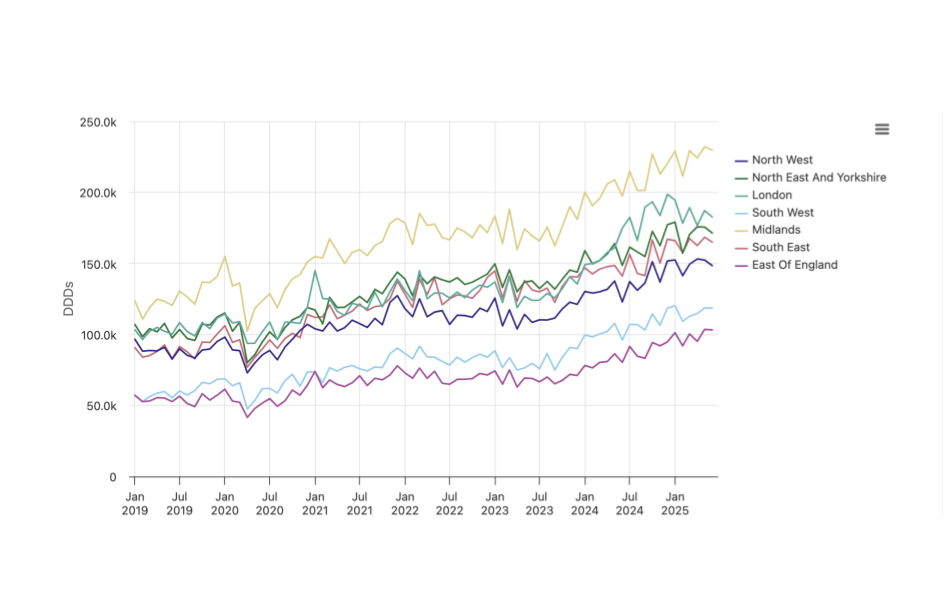
How you can run custom analyses of variation in medicines issuing across NHS trusts, ICB, region and nationally.

A summary of our research letter highlighting continuing co-proxamol use, published in the British Journal of General Practice
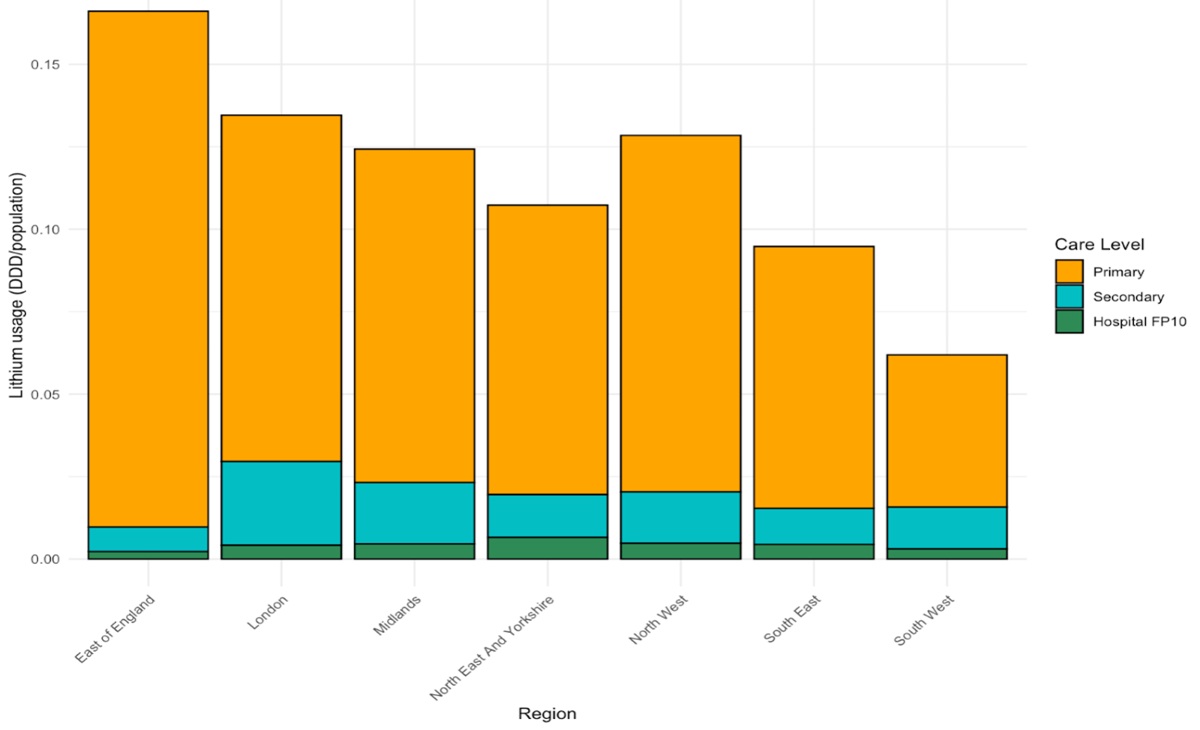
A national medicines usage analysis for lithium in primary and secondary care in England
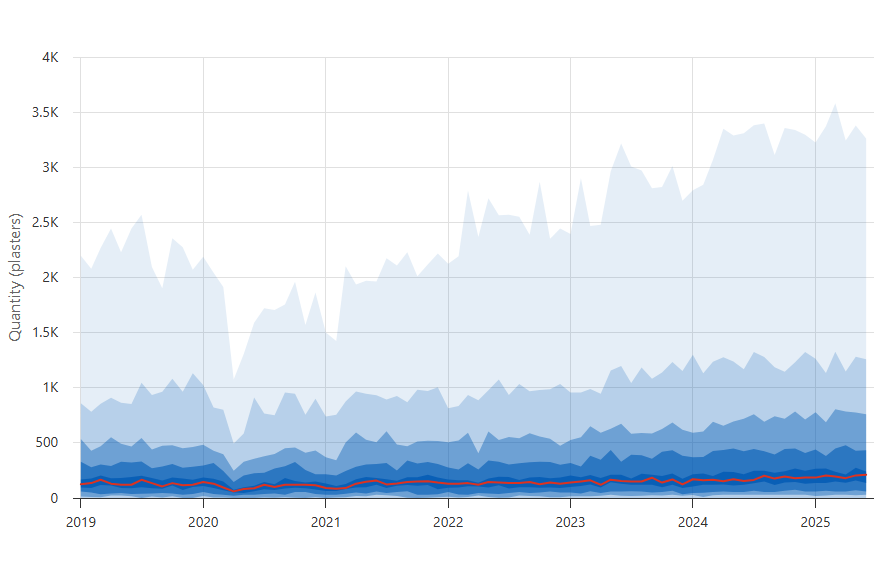
We’ve launched a new OpenPrescribing Hospitals ‘low value prescribing’ measure for lidocaine plasters.

Special edition OpenPrescribing newsletter introducing our new tool, OpenPrescribing Hospitals.
We’re launching the Bennett Prize in OpenPrescribing to celebrate the best user-led projects using OpenPrescribing. Enter by sharing your work online and sending us the link — all kinds of entries welcome, from prescribing insights to data science deep dives.

What are biosimilars, why are they of interest and why can we monitor usage with primary care data but not secondary care data?
In this guest blog, Dr Christianne Micallef explains how she uses OpenPrescribing in her role as an antimicrobial stewardship lead pharmacist.
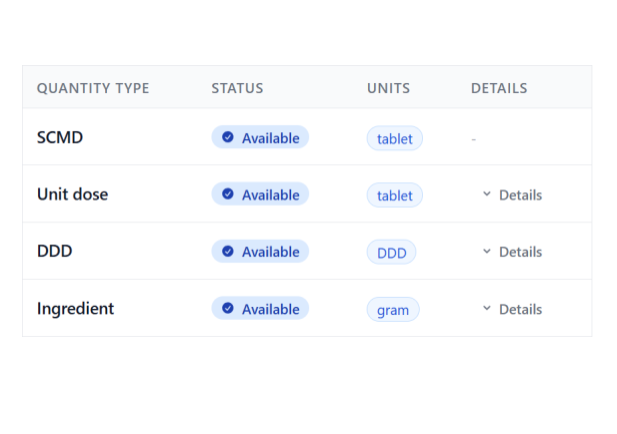
A look at the new Product Lookup feature on OpenPrescribing Hospitals
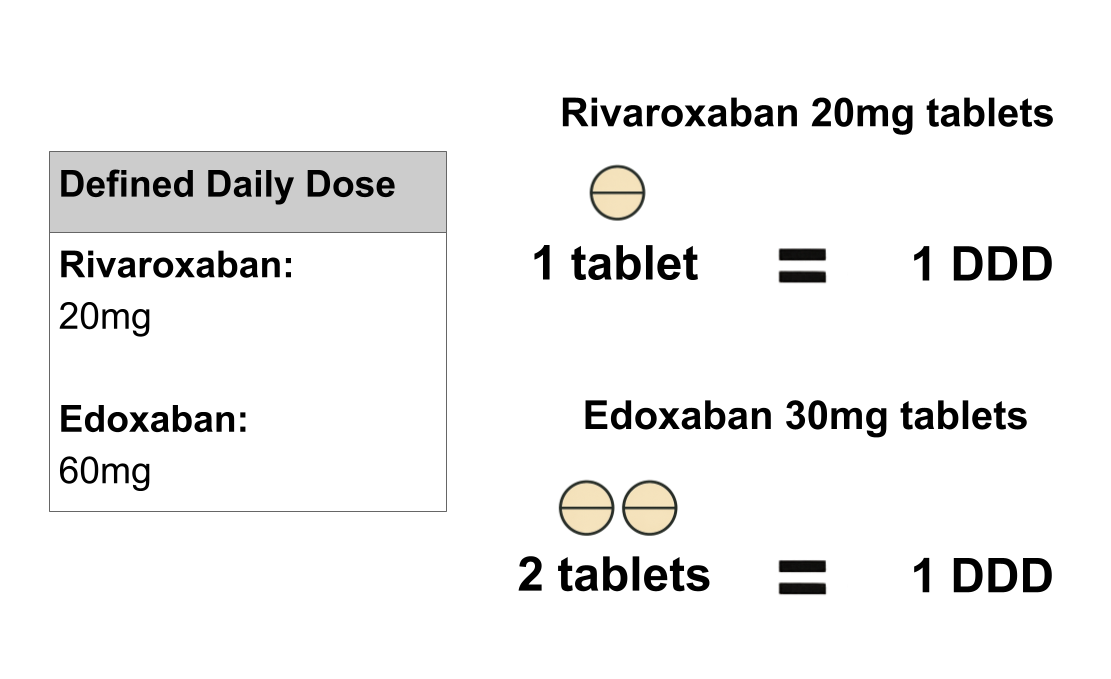
What is a Defined Daily Dose, how can they calculated from the quantity reported in the Secondary Care Medicines Data, and why are they useful?
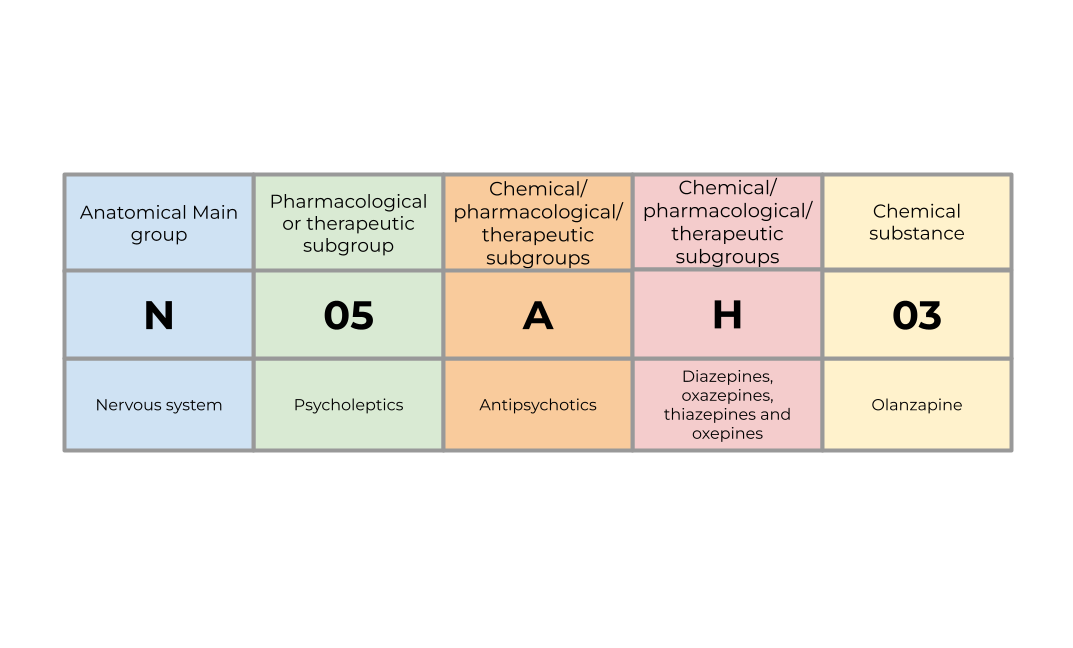
How the ATC can be used to classify medications and how DDs can be used to measure their usage.
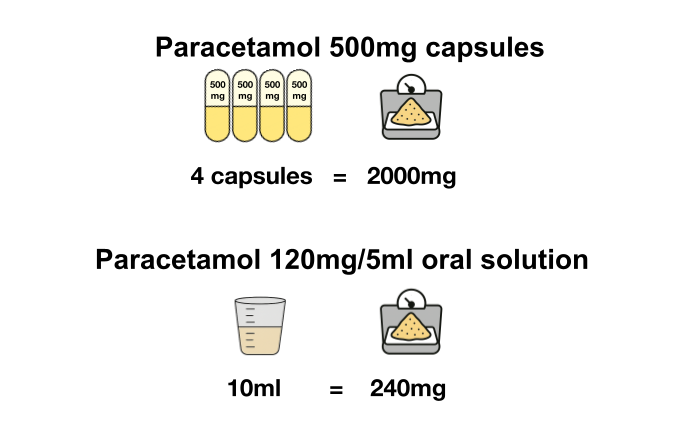
What is ingredient quantity, how can it be calculated from the quantity reported in the Secondary Care Medicines Data, and why is it useful?

In 2019, we pitched a national tool to track local formularies. Now the NHS is doing just that! We’re sharing our plans and advice to help it succeed.

What are unit doses, how can they be calculated from the quantity reported in the Secondary Care Medicines Data, and why are they useful?
A look at how quantity is measured in the Secondary Care Medicines Data
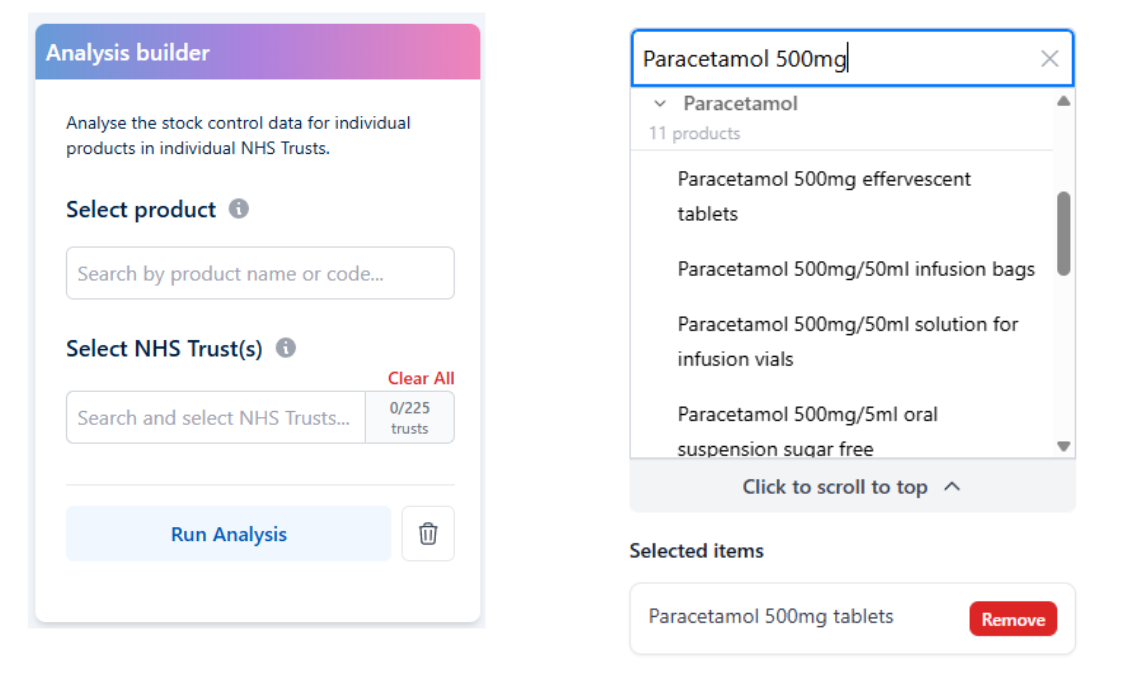
The new custom analysis feature on OpenPrescribing Hospitals.

How we can use OpenPrescribing Hospitals measures to look at use of low value medicines in hospitals.
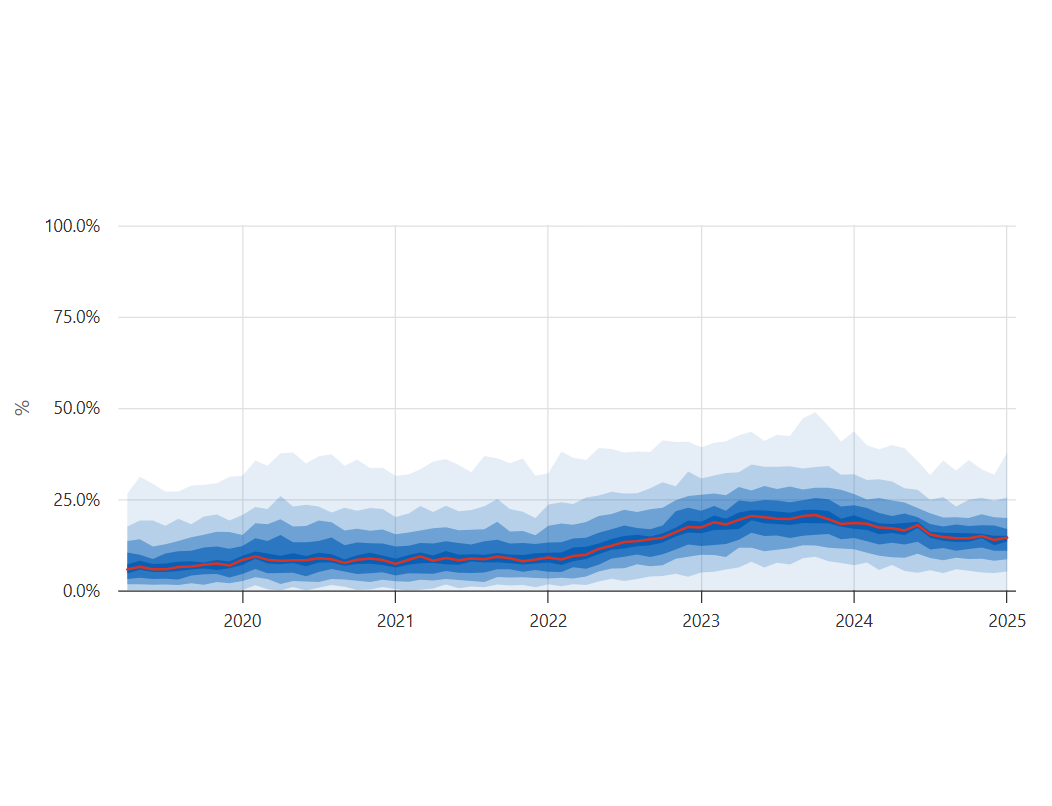
How we highlight variation in hospital medicines usage in OpenPrescribing Hospitals Measures.
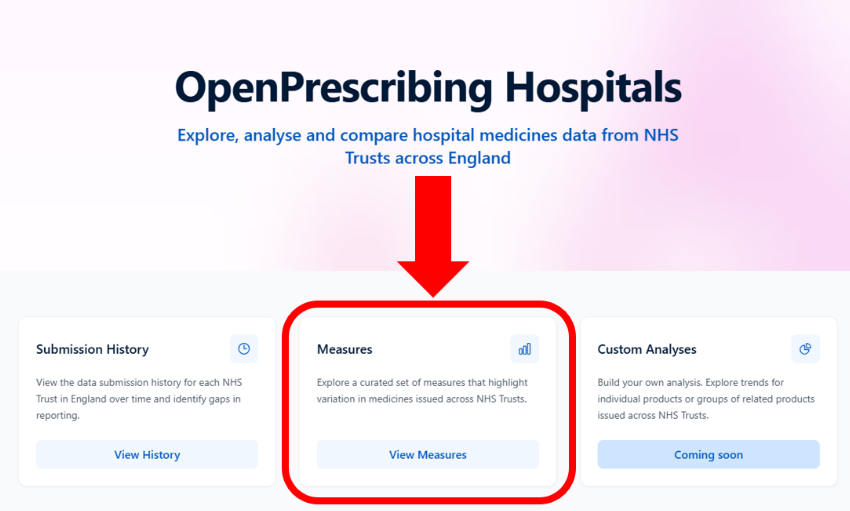
An introduction to a new measures tool in OpenPrescribing Hospital.

The way the Secondary Care Medicines Data is published has recently changed. This is why this is good news for OpenPrescribing Hospitals.
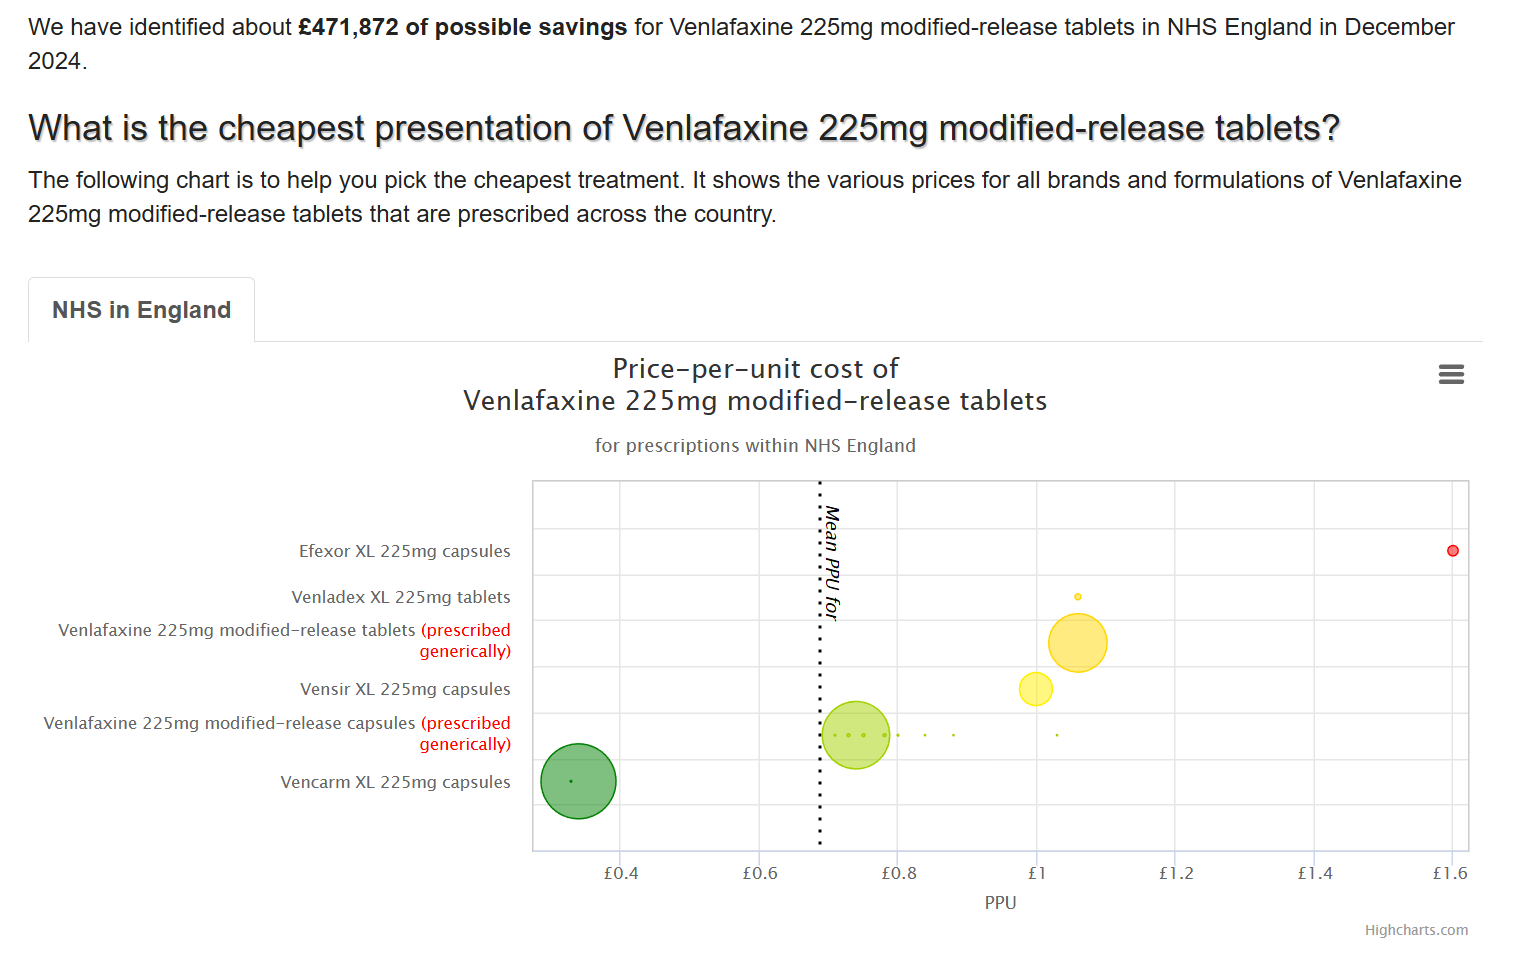
This blog explains the major changes we’ve made to how the Price-Per-Unit tool works
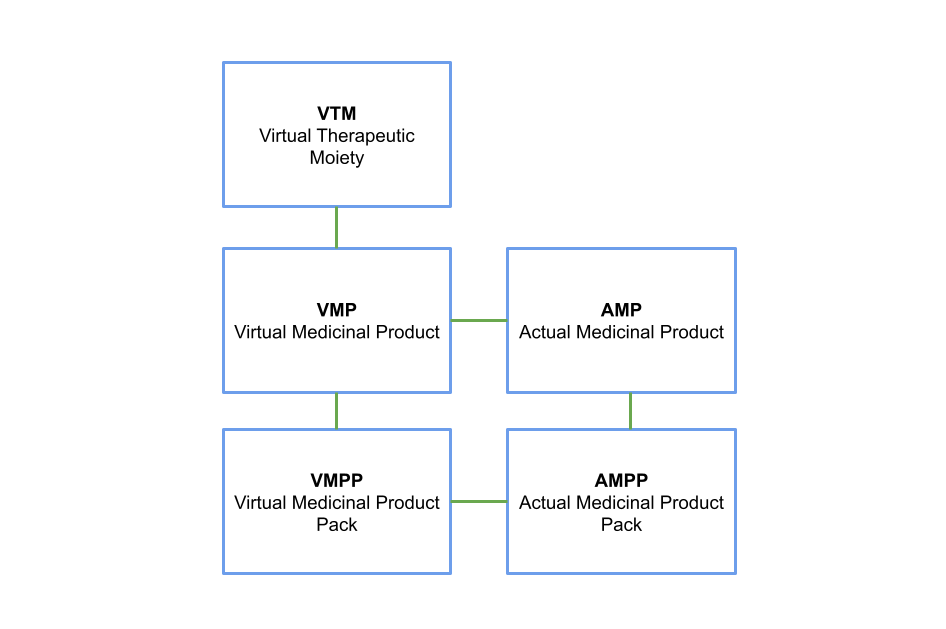
How we can make it easier to compare issuing quantities of different products within the Secondary Care Medicines Data by using the dictionary of medicines and devices to find more detailed product information.
A first look at the data within the Secondary Care Medicines Dataset.

We’ve made OpenPrescribing Hospitals platform to all with our first feature. Read more to see how you can access it.

A deeper dive into what stock control data is and how it impacts the way the SCMD is published
A brief description of the Secondary Care Medicines Dataset, the primary dataset used in OpenPrescribing Hospitals

An explanation of the Submission History feature on OpenPrescribing Hospitals
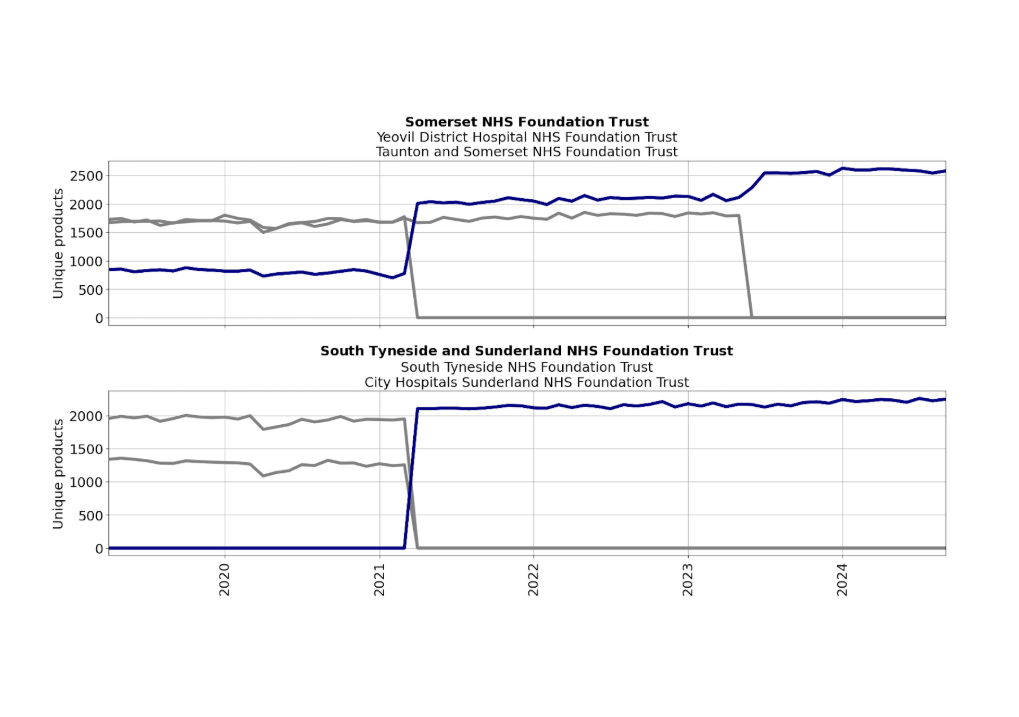
The third blog in the series: Organising Organisations. Here, we describe how consistent the data submitted by NHS Trusts to the Secondary Care Medicines Dataset is
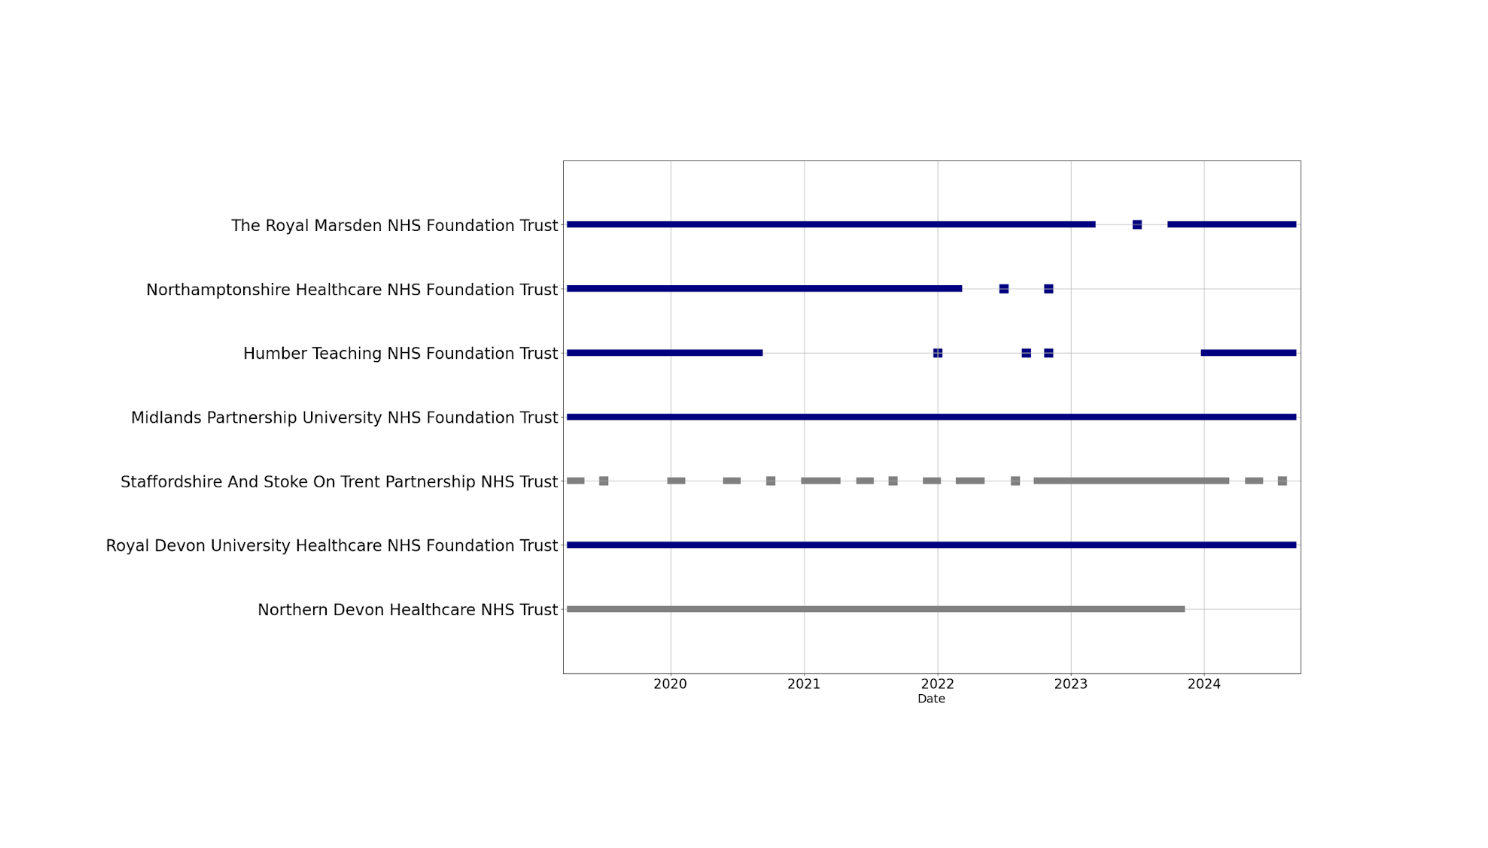
The second blog in the series: Organising Organisations. Here, we describe how complete the data submitted by NHS Trusts to the Secondary Care Medicines Dataset is
The first blog in the series: Organising Organisations. Here, we describe which NHS Trusts are included in the Secondary Care Medicines Dataset and how they can be identified

Here we describe how to access and use the Low Value Prescribing dashboard on OpenPrescribing.

We’re going to build OpenPrescribing for hospitals using openly available secondary care medicines data. Here we explain why and what you can expect.

If you didn’t manage to attend the OpenPrescribing antimicrobial stewardship webinar, don’t worry! You can watch it back here.

An updated best-value DOAC measure, developments in hospital medicines data, webinar recordings, and an analysis of OpenPrescribing’s users.
Catch up with our OpenPrescribing webinars

We are hosting a webinar special in support of World Antimicrobial Resistance Awareness Week 2024
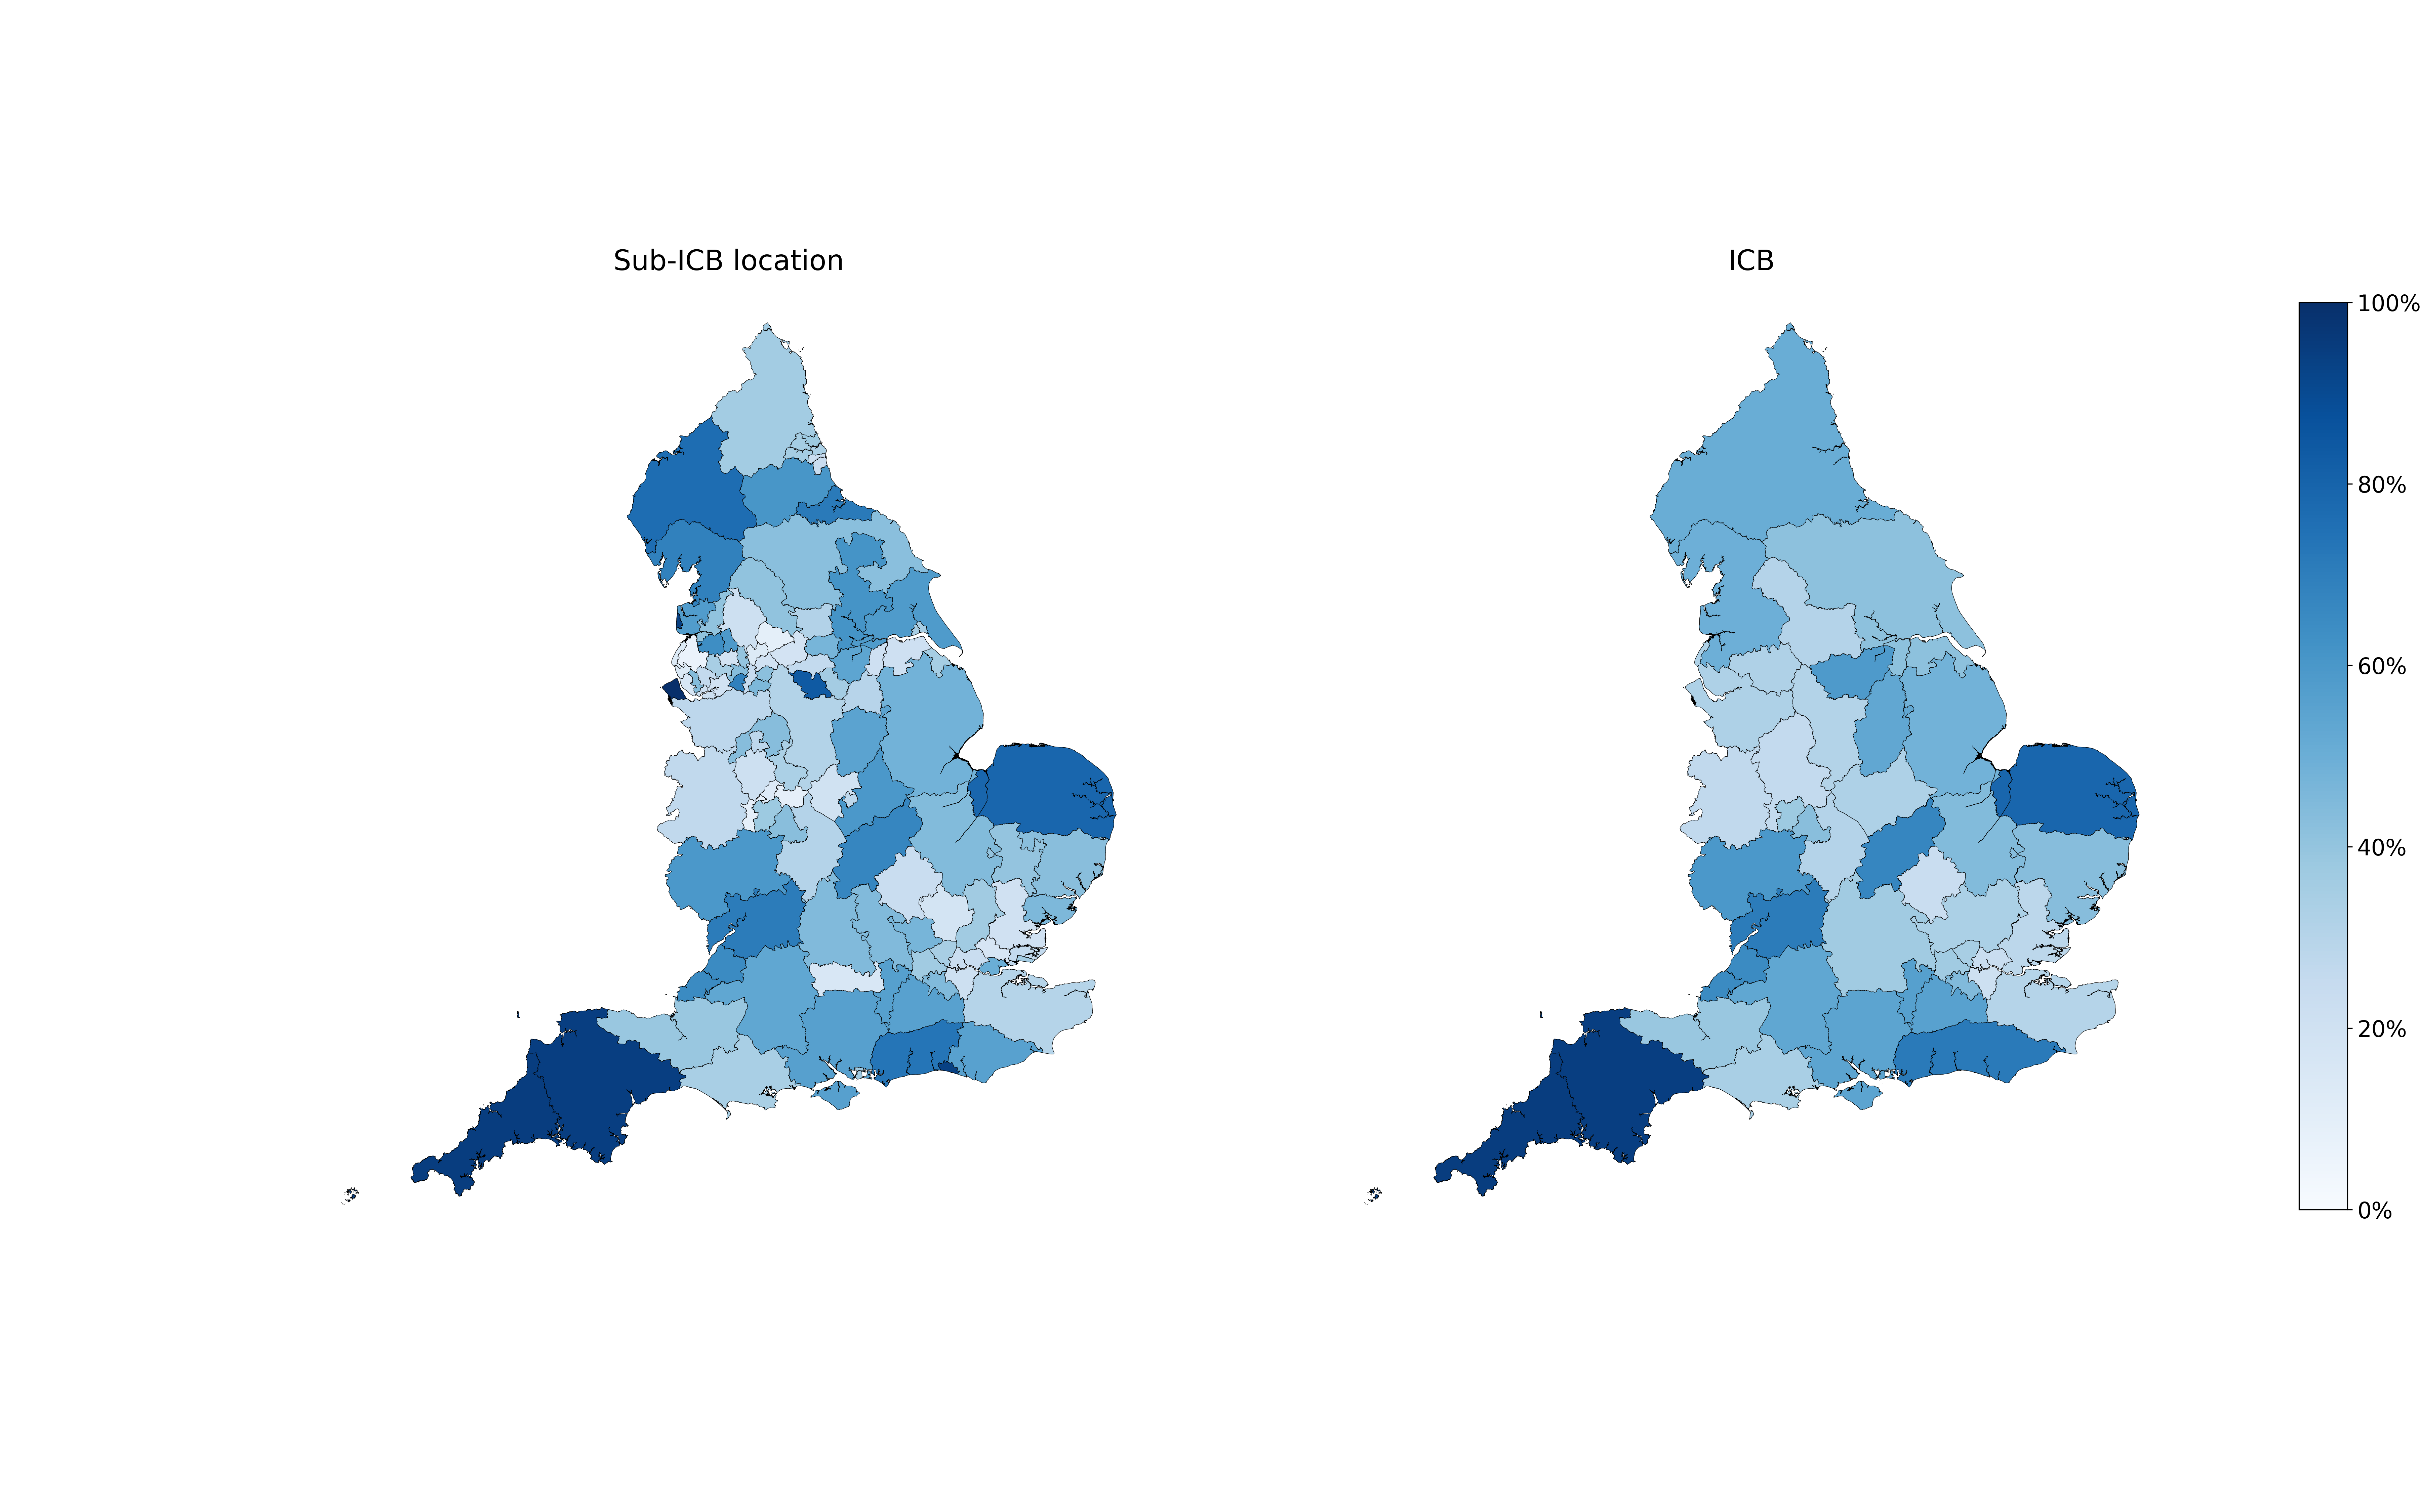
We’ve analysed what we know about our OpenPrescribing user base. Here’s some information obout how many of you there are, what you all look at, and which organisations have signed up to our alerts.
We’ve updated the DOAC measure following changes to the NHS England commissioning guidance.

We briefly summarise all the recent big and exciting developments in hospital medicines data.

Free OpenPrescribing webinars, plans to phase out STAR-PUs, and updates to the excess pen quantities measure and price concession calculations.

We’ve been producing estimates on the impact of Price Concessions since 2017. In this blog we describe the changes we’re making in how we estimate the costs.

We’re setting up webinars for different groups to show how to use OpenPrescribing effectively. Each session will cover the basics and tips for getting the most out of it.

We describe the reasons why people sometimes find a medicine on OpenPrescribing.
In this guest blog, Molly Mattsson describes how we compared lidocaine prescribing reduction policy implementation in Ireland and England.

Debating STAR-PUs, launching Improvement Radar to identify prescribing improvements, and research on medication reviews during COVID-19.

We’ve launched a new OpenPrescribing tool, the Improvement Radar, which makes it easy to identify organisations which have shown substantial improvement.

In this blog we explain some of the issues with using STAR-PUs and ask for your input on how we should use them in future.

Why prescribing analyses differ between platforms, a BNF-to-dm+d map, and updates to antibiotic and glucose test strip measures.

In the second of a two-part blog we explain why OpenPrescribing figures don’t always match with other prescribing data resources, due to differences in how data is presented.

In the first of a two-part blog we explain why OpenPrescribing figures don’t always match with other prescribing data resources, due to differences in the data source.

This blog describes how we develop new measures at OpenPrescribing.

The second session in the Bennett Conference was a series of talks covering the history, technical underpinnings, research and use cases of OpenPrescribing.

A whistlestop tour of the whole history of our group, from OpenPrescribing via TrialsTracker to OpenSAFELY and on through Open Science, policy work, and more

A common question asked of the Bennett Institute is ‘have you got a tool to map BNF codes to dm+d codes?’ We’ve created one to download

We’ve been busy creating new measures for OpenPrescribing.net, and reviewing ones which aren’t needed any more.

We’ve been busy doing housekeeping on OpenPrescribing.net measures. Here’s a summary of the main changes.

NHS medicines optimisation tools, an investigation into rising colesevelam costs, and a look at the pharmacists behind OpenPrescribing.
In this blog, we describe how OpenPrescribing tools helped identify and investigate a sudden £450k per month increase in NHS expenditure

In this blog we describe how to use and access the NHS England Medicines Optimisation Oppurtunitites dashboard on OpenPrescribing

At the Bennett Institute for Applied Data Science we’re always pleased to see stories in the media which have used OpenPrescribing.net. Here are some of the highlights of stories that we have been featured in recently.

Here we introduce the Bennett Institute’s Clinical Informatics team, explaining what they do and how their experience in NHS clinical practice helps them do this.

One of our key aims at Bennett Institute for Applied Data Science is to develop novel data-driven approaches to interpret our health care data. We want to use data science to identify patterns in the data that afford us a new, unbiased perspective on how well the NHS is working and how it could be better.

Bennett Institute resident pharmacist Brian MacKenna sets out some brief information on how we currently build medicines codelists on OpenSAFELY.
The launch of the Bennett Institute, the Goldacre Review, live Outlier Detection Dashboards, and new measures for DOACs and inhaler carbon footprints.

We have a new tool available at OpenPrescribing: our outlier prescribing dashboards will show you what your favourite CCG, PCN, STP or practice are prescribing more (or less) than everyone else. Read more about how it works and how to use it here.
Previewing the Outlier Prescribing tool, updating measures and maps, and research on antidepressant prescribing and anticoagulant safety.

Applications closed. Clinical Informatician role in the Open Analytics Unit, translating clinical knowledge into NHS data analysis and open tools.

Recently we started reviewing a number of measures that needed the most urgent attention. As a result a number have been updated and a couple have been retired.
Retiring the hospital-only measure, updating oral morphine equivalence, introducing OpenCodelists, and reporting COVID-19 vaccine coverage.

Applications closed. Epidemiologist / Health Data Scientist role using OpenSAFELY to study the impact of COVID-19 on patients and health services.

Applications closed. Platform Lead role combining Python development, software architecture and engineering leadership for OpenSAFELY.
New hospital medicines data, plans for OpenPrescribing Hospitals, research on clinical software design, and an oral morphine equivalence update.

In July, Ben and Brian wrote a piece in the British Medical Journal arguing that hospital medicines data should be openly shared. Magnificently, the NHS has now made secondary care medicines data (SCMD) available. You can read the full technical specification of the data here but briefly: it is hospital pharmacy stock control data, which is collected and processed by Rx-Info, and is now published on the NHS Business Services Authority website in the NHS dm+d standard we know, love, and have documented well.

This is the website code for openprescribing.net - a Django application that provides a REST API and dashboards for the English Prescribing Dataset published by the NHS Business Services Authority. Information about data sources used on OpenPrescribing can be found here.
New papers on hospital medicines data, NHS analytics and statin prescribing, alongside updated CCG dashboards and OpenSAFELY COVID-19 research.

Update May 2021 Based on feedback received from users, the NHS dictionary of medicines and devices has decided to cease maintenance of the “hospital only” value at AMP level (it remains at AMPP level). As a result this means that we are no longer able to produce our “Hospital Only measure” and we have retired it.
Just prior to the COVID-19 emergency we launched a new measure on OpenPrescribing, primary care prescribing of medicines defined by the NHS dictionary of medicines (dm+d) and devices as “hospital only”. In this blog we set out what exactly this means, describe some of our early investigations and interesting (but nerdy) details, and ask for your help in improving and maintaining this dm+d field.
A guest blog from Dr. Kevin Barrett (Twitter @DrKBarrett).
Last week the British Journal of General Practice published our paper on unsafe prescribing of methotrexate. As part of the publication Dr. Kevin Barrett talked to BJGP (see video below) about how he used OpenPrescribing to identify potentially unsafe prescribing in his practice and has also written a short blog below.
When I first started as a GP trainee in 1999 electronic prescribing was a relatively recent innovation. The practice formulary was built by hand, and prescribing analysis only occurred when paper Prescribing Analysis and CosT (PACT) reports were sent to the practice. These evolved into ePACT reports, but these still required time to decipher. With the advent of Primary Care Trust (PCT) and then Clinical Commissioning Group (CCG) employed pharmacists who had the time to analyse the data and present practice- and prescriber-level data to us at a range of meetings we became used to comparing our prescribing data to our peers. Electronic prescribing aids are a useful measure to help guide our prescribing and keep us up to date with the ever-changing local and national recommendations.
New research on unsafe methotrexate prescribing, bespoke prescribing email alerts, and analysis of COVID-19’s impact on prescribing in March 2020.
At OpenPrescribing we know that clinicians can be overwhelmed with guidance and data about many different aspects of care. We therefore have developed an innovative email alert service for every single practice, primary care network and clinical commissioning group in England that delivers bespoke custom emails to your inbox about your own organisations prescribing.
To sign up to your organisation’s alerts all you need to do is:
These email alerts help people keep track of their prescribing trends, alert you to changes in prescribing that may be difficult to spot and importantly tell you if your prescribing has changed in comparison to your peers. You can see an example of an OpenPrescribing practice email alert here and you can read more about the methods in our paper.
Introducing OpenSAFELY, COVID-19’s early impact on prescribing, rising price concession costs, and bespoke PCN email alerts.
OpenPrescribing.net has been updated this week with the latest release of prescribing data covering March 2020. In-depth analysis will be needed over the coming months, but this release gives us the first glimpse into the impact that COVID-19 has had on prescribing. At the Bennett Institute we have been quite busy with the new secure analytics platform OpenSAFELY but the following blog is a rapid analysis of the March prescribing data which others may find helpful to focus their own investigations. As always, all our analytical code is openly available on our GitHub for inspection and reuse by anyone.

The following is a rapid analysis of the “top 10” medicines in NHS England primary care in 2019. We prepared this analysis for a user who wanted to use the list in a teaching session with students to prepare them for the medicines they will most commonly see in general practice. We are sure others will find it useful — please get in touch and tell us how you use it via Twitter or feedback@openprescribing.net. As always our analysis with complete analytical code is openly available on our GitHub page. You can also investigate the prescribing of any medicines you like using our tools like our Analyse page, chemical trends and our brand new browser for the NHS Dictionary of Medicines and Devices. Read on below where we describe the “top 10” medicines and class of medicines, in terms of volume and cost.
At the Bennett Institute we like to work in the open and share our insights for the whole community, so we can fix a problem for us, then share the solution, and help fix it for everyone. We think this is efficient for us and the whole system. In this blog our magnificent coder Peter Inglesby sets out some analysis he has done of changes to the NHS prescribing data we use. It took us a few hours to investigate these problems for our own purposes, then document our findings and solutions internally; it took an extra 20 minutes to share in this blog post and now we give it to you so you don’t have to replicate our effort and can maybe find some insights we have missed!
Update September 2020: NHS England have announced a reduction in the number of planned measures including the majority of the measures on OpenPrescribing. We will remove the IIF dashboard in a future update.
Update: Due to COVID19 response NHS England has announced that the IIF will be postponed. We will continue to make this dashboard available as NHS England also states that they will continue to monitor the data to understand any impact.

At the Bennett Institute we get many people contacting us every month asking us when OpenPrescribing will be available in their country. In this blog we are outlining OpenPrescribing.yourcountry where we give you the information that you can use locally to build a case for OpenPrescribing in your country and obtain funding to support development. We aren’t quite ready to build OpenPrescribing.yourcountry yet, but we will be soon and we wanted to share our plans so you can be ready when we are.

Most people share their end of year roundup during late December when everyone is too full of cake to read. Now you’re back in the saddle, here’s our roundup of everything the Bennett Institute threw out into the world over the previous 12 months!
OpenPrescribing.net went from strength to strength, with over 135,000 unique users last year. We now have over 80 measures of prescribing safety, efficacy and cost-effectiveness and have been working on new types of measures and alerts to identify “outlier” prescribing, such as with zuclopenthixol. In 2019 we also: launched new dashboards and bespoke alerts for every single primary care network (PCN), sustainability and transformation partnership (STP), and NHS region; upgraded the Analyse page to support more organisations with bespoke medicines queries; and developed tools to help solve the problem of Ghost Branded Generics which cost the NHS an extra £11.6million per annum but has massively reduced during 2019.

Today on OpenPrescribing.net we have launched our Greener NHS prescribing dashboards. Over recent months there has been increasing attention on the environment and the effects society is having on climate change. The NHS announced specific targets as part of its long term plan to become more sustainable, reduce waste and shift to lower carbon inhalers. At OpenPrescribing we have already launched our first prescribing measure related to the environment and this week we are launching our Greener NHS prescribing dashboard for every single general practice, primary care network (PCN), clinical commissioning group (CCG), sustainability and transformation partnership (STP), NHS region and for the whole of England.To access your Greener NHS prescribing dashboard, simply go to your organisation’s measures page and select “Greener NHS” from the drop-down. You can read more about our categories on our blog or watch our short Youtube video.

Today on OpenPrescribing.net we have launched our National Institute for Health and Care Excellence — NICE Prescribing Dashboard. We have a NICE prescribing dashboard for every single general practice, primary care network (PCN), clinical commissioning group (CCG), sustainability and transformation partnership (STP), NHS region and for the whole of England. This allows anyone to explore how NICE guidance has been implemented in their organisation, supporting effective, safer and more efficient prescribing. To access yours, simply go to your organisation’s measures page and select “NICE” from the drop-down. You can read more about our categories here or watch our short Youtube video:
PCN dashboards go live, research examines clinical software and prescribing safety, and a guest blog explores high-dose dexamethasone.
A guest blog from Calum Polwart (Twitter @ShinyBlackShoe)
At the Bennett Institute we value openness and transparency as we believe open discussion of ideas and methods are the key ingredients for high quality data analysis. We think it is unhelpful that so much NHS data analysis is outsourced, or done behind closed doors, as this prevents coalface clinicians from engaging with data and sharing their expertise and insights. We build OpenPrescribing.net, not just for ourselves, but for anyone to explore NHS prescribing data. This democratisation of prescribing data removes gatekeepers and barriers to accessing the data, allows anyone to scrutinise prescribing and produces new insights.
Today on OpenPrescribing.net we have launched our Primary Care Networks (PCNs) dashboard. We have PCN prescribing dashboards available for every single NHS PCN and their member general practices. This allows anyone to explore NHS prescribing patterns in their PCN and see how this compares to other PCNs across England — supporting safer, more efficient prescribing.
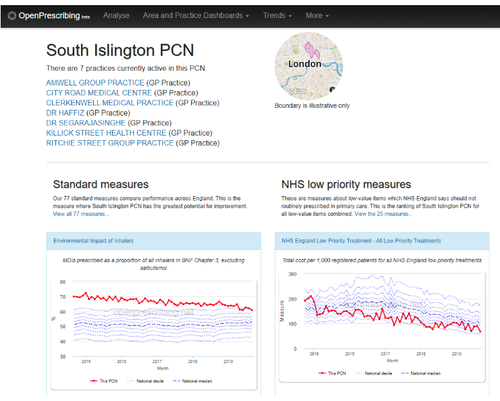
Figure 1: South Islington PCN OpenPrescribing Dashboard
PCNs are groups of practices, which together serve communities of around 30,000-50,000 people, with the aim of improving care for patients. PCNs were announced as part of the NHS long term plan and many PCNs have formed already and started to recruit staff such as clinical directors and clinical pharmacists to improve and optimise the use of medicines. We hope our PCN prescribing dashboards will assist everyone across the country to identify and prioritise areas where prescribing can be improved.
New inhaler environmental impact and seven-day prescribing measures, research on prescribing changes, and expanded data downloads.

At the Bennett Institute we regularly collaborate on projects, both small and large, with users who get in touch. For development of this measure we would like to thank the NHS England Sustainable Unit and Centre for Sustainable Healthcare for their input on our work to support the NHS Long Term Plan. Another one of our collaborators on this work is Nicola Read, a respiratory doctor who is currently one of the National Medical Director’s Clinical Fellows. Below we set our new measure on inhalers and the environment and Nicola explains its importance for all inhaler prescribers.
This week we launched a new measure of seven day prescription for medicines used to treat long-term conditions. There is no current consensus on duration of prescription across the NHS and prescribers are advised that they should write a prescription for a duration that is clinically appropriate. For medicines that are for stable long-term conditions many areas have policies in place recommending one, two, or three month prescriptions.
Medicines Compliance Aids (MCAs), sometimes known as dosette boxes or pill organisers, are plastic boxes with small compartments that show which pills need to be taken at what time of day. The British Medical Association reports growing requests to prescribe seven day quantities of medicines to fund supply of medicine compliance aids (MCAs). We propose this measure of seven day prescriptions for long-term conditions as a surrogate measure for MCAs.

Zuclopenthixol is an antipsychotic used for schizophrenia and other psychoses. In the UK, there are two injectable forms of zuclopenthixol:
This week we launched a new measure to support a new type of alert to identify any prescriptions of zuclopenthixol acetate for further investigation. It is not recommended to be prescribed in primary care, so prescriptions may have been prescribed in error.
Links from prescribing measures to the Analyse page, improvements to the price-per-unit savings tool, and preparations for PCN dashboards.
The launch of the NHS dm+d browser, lower thresholds for price-per-unit savings, and price concession dashboards for STPs and regional teams.

This week we have launched a new browser for the NHS Dictionary of Medicines and Devices, better known as dm+d. dm+d is the standard dictionary for the medicines and devices used across the NHS. It contains codes and descriptions for all these medicines and devices; at last count there were over 150,000 packs of medicines and devices described. You can read more about the dm+d in this detailed blog.
Our dm+d browser allows anyone to search and identify any product in the NHS. For example, you can see all the paracetamol products available in the dm+d here. We’ve previously written about how the dm+d can be useful, like using user-friendly names on the website, or identifying all dry powdered inhalers for analysis. As we have found our dm+d browser so useful, we believe others will find it useful too, and have now made it available publicly for anyone to use.

Over the past year we have been increasingly using NHS Dictionary of Medicines and Devices (dm+d). This blog post sets out to describe dm+d for the benefit of the wider prescribing analytics community and others.
dm+d is the standard dictionary for the medicines and devices used across the NHS. It contains standardised codes, descriptions, and metadata (such as price and pack size) for every entry. At last count it contained over 150,000 packs of medicines and devices.
New low-priority prescribing measures and All England email alerts, alongside Analyse page improvements and plans for Primary Care Network dashboards.

Our technical team are busy improving how the engine room of OpenPrescribing. When they’ve finished we’ll get them to write a blog on exactly what they’ve done. In the meantime, as the work progresses we are able to add some additional exciting new features to the site.
One of the limitations of how our Analyse page worked was the ability to only search at one BNF level at a time. For example, you couldn’t search for products and presentations together. However, now you are able to add any combinations you want, making this tool much more powerful. For example, it’s helpful when looking at broad-spectrum antibiotics: previously you could only include either cephalosporins and quinolones (BNF paragraphs), OR co-amoxiclav (a BNF chemical). Now you can include all of them at the same time.

Update November 2019: Our NHS PCN dashboards are now live at https://openprescribing.net/pcn/ and you can read more on our launch blog.
Update August 2019: Our amazing developers have written all the code necessary to display all prescribing measures and data for all PCNs in England on OpenPrescribing. Unfortunately there is no national list of PCNs and their membership available, as soon as this is published we will bring you our prescribing dashboards.
Research on variation in adopting UTI prescribing guidance, user testing for regional and STP dashboards, and preparations for newly merged CCGs.

Just before Christmas we had a paper published in the Journal of Antimicrobial Chemotherapy. It looked at how GP practices responded to changes to the guidance for antibiotics for urinary tract infections (UTIs).
It’s an interesting story in itself, but we think that it prompts some wider questions about how GPs are helped to keep up-to-date on guidance on prescribing.
For many years the mainstay of antibiotic treatment of uncomplicated UTIs in women has been trimethoprim. Recently there has been growing concern about the increasing levels of resistance (about a third of urine samples).

This week we have launched a new email alerting service that covers all of NHS England. Many users of OpenPrescribing already receive our monthly newsletter and our innovative email alert service for practice and CCG prescribing measures and for price concessions. We have now developed this service covering all of England based on user feedback. To sign up, just go to the All England page and enter your email address in the box beside the measures categories (see screenshot below).

On OpenPrescribing.net we provide data for individual practices and CCGs (and now STPs and regions!) making it easier for everyone to explore NHS prescribing patterns in England - supporting safer, more efficient prescribing. However, providing data for an individual location in isolation is rarely useful. We need to provide context, so that some sort of judgement can be made about whether the prescribing in question is especially high or low, and how extreme it is, in comparison with others. On OpenPrescribing we do this using deciles. We think providing transparency in our methods is really important, so in this blog I set out our rationale for doing so.

At the Bennett Institute we value openness and transparency as we believe open discussion of ideas and methods are the key ingredients for high quality data analysis. We think it is unhelpful that so much NHS data analysis is outsourced, or done behind closed doors. This blog sets out the steps we take with OpenPrescribing.net to ensure all our analysis and methodology is freely available for inspection, review, and importantly re-use, by anyone. We hope other teams will adopt these approaches so we can all collaborate to optimise analysis, generate insights and improve care for patients in the NHS.

In the last year we estimate that price concessions have cost an additional £165 million in unplanned expenditure for Clinical Commissioning Groups (CCGs), and our OpenPrescribing.net price concession calculator was featured in a major BBC news story and in the Pharmaceutical Journal this week. However, interestingly, NHS price concessions do not just affect the NHS: they also represent unplanned expenditure for charities, local councils, and others. Here, we report our estimate of the impact on non-CCG organisations as an additional £5.6 million in 2018: a huge four-fold cost increase on top of expected prices for a sector that is already over-stretched.

Today we launched NHS regional and STP dashboards on <OpenPrescribing.net>, which allow anyone to see NHS prescribing patterns across areas larger than CCGs. You can find these new dashboards under “Area and Practice Dashboards”.

The NHS across England is now organised into Sustainability and Transformation Partnerships (STPs) and NHS England regions. There are 44 STPs made up of NHS organisations such as CCGs and hospital trusts, and local councils, who developed shared proposals to improve health and social care, whilst ensuring services are joined up across all of the organisations they incorporate. STPs are contained within the five NHS England regional teams; these teams support healthcare commissioning and delivery in their area by providing professional leadership on finance, nursing, medical, specialised commissioning, patients and information, human resources, organisational development, assurance and delivery.

At OpenPrescribing we have a range of prescribing measures that makes it easier for everyone to explore NHS prescribing patterns in England - supporting safer, more efficient prescribing. We now have 70 measures including our two latest on Freestyle Libre and herbal medicines, that we recently blogged about. The measures are available for for every single practice and CCG in England and cover a range of clinical areas such as medication safety and antimicrobial stewardship to support better prescribing.
New price concession email alerts, a guide to finding prescribing cost savings, and improvements to measure breakdowns and Analyse page totals.

Ghost Branded Generics are a relatively new category of cost-saving opportunities, caused by prescribers specifying a manufacturer for a generic product, often resulting in a higher reimbursement price compared to the true generic. We estimate the problem costs the NHS £11.6m a year. We have written about this extensively since our first blog on discovering the issue and developed a Ghost Branded Generics dashboard and measure for every practice and CCG in England.

Today we launched a new feature on OpenPrescribing: an NHS Price Concession email alerts service. This is in addition to our existing calculator that shows cost impact of price concessions, which can already be viewed on every practice, CCG and All England dashboard. You can read more about price concessions (aka NCSO) in our previous blogs.
Many users of OpenPrescribing receive our monthly newsletter and our innovative email alert service for practice and CCG prescribing measures. Today we are adding a new NHS Price Concession email alerts service. Once signed up, this alert will pop into your inbox a few hours after a new price concession is announced, which will be approximately once per week, to update you on the impact these costs are predicted to have on your practice/CCG.

…Identify CCG Cost Savings Opportunities using OpenPrescribing.net
Every year in the NHS local teams around the country put together “QIPP Plans”. QIPP stands for Quality, Innovation, Productivity and Prevention and is a large scale programme introduced across the NHS to ensure the NHS delivers more for the same funding. We make no comment on the programme itself but we think OpenPrescribing is a useful tool in helping develop “QIPP Plans” and to identify new areas for savings related to medicines spend.

We have recently released two new measures on OpenPrescribing — the prescribing costs of herbal medicines, and the quantity of Freestyle Libre.
For techie reasons, we’re quite excited about the herbal medicines measure. We don’t like to write measures that require a manually managed list of preparations, as these require a lot of curation, and can quickly become inaccurate if a new drug is released. Therefore for most (if not all) of our measures we use the hierarchical BNF codes provided by the NHS Business Services Authority (you can read more on these here).

While investigating the data behind Ghost Branded Generics, we came across something that we didn’t expect. As part of our work in creating the Drug Tariff viewer (once we’d managed to obtain the data), we’ve got an archive of Drug Tariff (DT) prices going back to 2010. We used our DT archive to compare listed reimbursement prices with what was actually being paid for generics, we sometimes found that the price paid wasn’t the one listed in the tariff. Instead, sometimes the price was based on the drug tariff price…from the future. or to be more precise, one month into the future.
Before Christmas we wrote about Ghost Branded Generics, a very nerdy story about a problem we uncovered that costs the NHS………£11.6million a year. Since then we have launched a freely accessible Ghost Branded Generics dashboard on Openprescribing.net for every practice and CCG in the country; and a Ghost Branded Generics measure so practices and CCGs can track their prescribing of Ghost Branded Generics over time.
We have also had lots of people get in touch about this whole new category of NHS savings. In particular we were contacted by TPP who produce SystmOne, the “electronic health record” (EHR) system used by approximately 40% of GPs in England.
Before Christmas we wrote a nerdy story about Ghost Branded Generics, a problem that costs the NHS £11.6m a year due to prescribers selecting specific manufacturer’s products rather than true generics. This is largely avoidable. Today we launch our Ghost Branded Generics dashboard for every practice and CCG in the country. This can be accessed through every dashboard page (example below) and we think it will be useful to help people change prescriptions from Ghost Branded Generics to true generic prescriptions.

This a very nerdy story about a problem that costs the NHS £11.6m a year. It shows how one small design choice in the software GPs use can have huge ramifications for how we prescribe, and a huge cost impact on the NHS. More than that, it shows how problems like these can only be spotted, and addressed, by mixed teams like ours — doctors, pharmacists, researchers and software engineers — pooling our different skills to build tools and papers.

Each year, we estimate there are up to £5m of Out of Pocket Expenses (OOPE) expenses charged to the NHS, added by dispensing contractors to their invoices. Could some of these expenses be reduced? In 2014/15 NHS Islington CCG wrote to dispensing contractors highlighting such expenses, and from this single intervention achieved a 50% reduction; spread across the country this could amount to a saving of £2.5m.
We’ve done some initial investigations, but don’t have resources to follow up in detail. This post is to note what we’ve found so far. If you are interested in finding out more, and have access to funding, let us know!

In our third full year of existence we produced even more exciting outputs and continued to grow. We welcomed Lydia Berry, back from maternity leave; Dave Evans, Consultant Programmer, who joined the OpenPrescribing technical team; and Brian MacKenna, an Honorary Research Fellow Pharmacist and member of the NHS England Medicines and Diagnostics Policy Unit. We also welcomed Darren Smyth, a UK and European Patent Attorney - our work so far includes our pregabalin papers (here and here), and he has also contributed to our EUCTR work.
New measures for NHS England’s proposed do-not-prescribe list, a planned price concessions calculator, and prescribing data limitations.

This week we launched a new feature on OpenPrescribing, an NHS Price Concession calculator. We show the cost impact of price concessions for the whole of England here and the calculator appears on every single practice and CCG dashboard so you can work out the impact locally.

Price concessions are a short term agreement by the NHS to pay more than the already agreed price for a generic medicine because pharmacists are unable to obtain the generic at its usual price. Regular readers of our blog will remember a series of blogs last year (see archive) where we detailed the issues and this led to the development of our magnificent Drug Tariff and Concession Viewer, which shows the prices over time for each individual drug, automatically updated on a daily basis.

Earlier this week NHS England announced a new “Do Not Prescribe” list for consultation.
Within an hour we made graphs showing every GP practice’s prescribing of these items. You can drill down to CCG level, and then practice level.
We hope that this data will be useful for clinicians and CCG pharmacists to identify where there is most room for improvement, or change. Or, to drive discussion about agreement on the guidance.

The data that drives OpenPrescribing is described briefly in our FAQ. It is supplied by NHSBSA and NHS Digital, and a few other sources.
Over the years we have come to understand the limitations of this data. We’re sharing them here, so researchers can take them into account when carrying out analyses.
When using Practice Level Prescribing Data, bear in mind:
When using list size (e.g. as denominator):
The launch of the All England dashboard, support for responding to phenytoin supply disruption, and tools for antimicrobial stewardship.
Drug supply issues are an interesting use-case for OpenPrescribing. Here we will talk about a recent example.
Last week the Department of Health and Social Care issued a “Supply Disruption Alert” for Epanutin (phenytoin) 30mg/5ml oral suspension: Pfizer, the manufacturer, will be out of stock of this product from the week commencing 29th October (today) until early December 2018. This means people currently taking Epanutin (phenytoin) 30mg/5ml oral suspension may need to be prescribed a different product.

This week we have launched a new page on OpenPrescribing.net, the All England dashboard, that allows anyone to see the quality of prescribing at a national level. For the first time we have aggregated all the savings from all our measures in one place. For the month of August these numbers are quite staggering:
£13,190,000 - could potentially have been saved if CCGs used our innovative price-per-unit tool (you can read our methods paper here).
Last week, a pharmacist from NHS North Cumbria CCG got our attention by mentioning OpenPrescribing on Twitter. He had just received a letter about a product for treating haemorrhoids called Uniroid. It’s a 50/50 mixture of Cinchocaine and Hydrocortisone, and is also available as Proctosedyl (made by Sanofi), and as a generic (i.e. unbranded) product.
The maker of Uniroid wants North Cumbria to start prescribing Uniroid-branded products, on the grounds it will save the CCG about £11,000 per year.
Recently we created antimicrobial stewardship dashboards for every Clinical Commissioning Group and General Practice in England by grouping our measures (see our blog post here).
We received feedback from users that some of our measures are difficult to understand, because they exhibit a high level of seasonal variation. Antibiotics show the most seasonality amongst our measures (e.g. openprescribing.net/measure/ktt9_antibiotics). As you can see below, it takes a lot of staring at this graph to work out whether the deciles (blue lines) are going up or down overall, and whether the red line (the data from a single CCG) is changing in relation to them.
How OpenPrescribing’s alerts detect changes before practices become extreme outliers, plus new category filters for prescribing measures.

Update: You can view a short Youtube video demonstrating this feature here.
On our OpenPrescribing CCG and practice dashboards you can now filter measures by category to view a small group of related measures together.
You can select a category using the new dropdown menu above the measures…

…Or by clicking on a category listed at the bottom of the description of a measure.

Upon selecting a category you’ll see its description / rationale above the measures:
New research examines pregabalin patent litigation and Lyrica prescribing, alongside site improvements that flag closed or dormant practices.
Research on low-priority prescribing, 2017 data in the Long Term Trends tool, and a call for measures highlighting easy prescribing improvements.
This is a brief blog about something small and trivial, but also big and important.
Recently on the staircase my friend Carl Heneghan came out with a good line about “Patient and Public Involvement”, or “PPI” as it is known in the trade. “People talk about PPI,” he said: “but we need PPPI… patients, the public, and professionals.”
I think this is absolutely correct. In academia, we often fail to focus on what happens at the coalface. In the Bennett Institute we’ve worked hard to change that. We take conventional academic funder money, and health data, and we produce conventional academic papers (by the shovel-load). But we also turn that data and person-time into live, interactive, data-driven tools like OpenPrescribing.net which people can hold in their hands, and use at the coalface to improve patient care.
New research on homeopathy and gluten-free prescribing, plus tips for using the Analyse page to investigate prescribing variation and trends.
An update on medicine price concessions, preparations for CCG mergers, and early work on OpenPathology to explore NHS blood test use.
The Pharmaceutical Services Negotiating Committee (PSNC) have released 3 sets of price concession price lists for February 2018. Once again, the total amount for England for the month has reduced: we’ve estimated the impact as £9.37 million for February 2018, although this is based on December 2017 data (the latest we have), and is therefore likely to reduce slightly (as February has fewer days).
The total for 2017-18 so far is £308.7 million, although the further impact is probably greater as some formerly low-cost generics are not considerably more expensive. For example levetiracetam 1g tablets, used in epilepsy, were £5.49/60 in July 2017, and in January 2018, following a spell as a price concession, increased to £36.07/tablets.
Here at the Bennett Institute we are a truly multidisciplinary team: clinicians, academics and software engineers, working together to produce tools, as well as papers.
This is glorious fun, and productive. From our time working together as a team we now have software engineers who know about clinical trials, prescribing data, and more; and we have researchers and clinicians who know a bit about building websites.
This may or may not thrill you, but I will share it: our academics write code that runs live on our websites! In addition, our team can be creative, because we all know a little about each others’ work: about what is possible with software and data, and what kinds of problem need solving in medicine.
A new opioid measure using oral morphine equivalents, improvements to the Long Term Trends tool, and the launch of the FDAAA TrialsTracker.
The latest price concession information for January has been released by the PSNC (in fact, two sets of data in quick succession). The PSNC have also stated that they are “still in discussion with the DHSC regarding further January 2018 price concessions”. Therefore we have made some calculations based on what we know at the moment - as soon as there are changes we will update this blog. UPDATE: We’ve now updated the data, both with the final concessions list for January 2018, and the actual cost data for December 2017.
We’ve been thinking in the Bennett Institute about doing stories, using our prescribing data, to go with landmark clinical trials and systematic reviews. Here’s an example.
A new systematic review published this week in JAMA shows that Omega-3 “fish oil” pills don’t really help improve cardiovascular health. As a systematic review, it’s a very useful overview of previous existing research. Perhaps reassuringly, as that evidence accumulated over time, clinicians were already changing their prescribing behaviour. Here’s the long-term NHS prescribing data from our database: NHS doctors gradually began to reduce prescribing of omega-3 a long time ago. Peak omega-3 was 2011!
The continuing cost of generic medicine price concessions, variation in gluten-free food prescribing, and a guide to OpenPrescribing’s features.
Everyone at the Bennett Institute wishes you a very Happy New Year!
Unfortunately, the NHS is still having the same problems in sourcing generics. The PSNC have just announced the latest list of price concessions for December 2017. The list was slightly smaller than November’s, with 86 lines,but we are still estimating an monthly impact for the NHS in December of £27 million. This brings the total excess cost for the nine months to December to £285 million:
Many people I’ve spoken to aren’t aware that gluten-free foods can be prescribed, but it happens quite extensively in an effort to help patients with coeliac disease adhere to a gluten-free diet.
Below is a chart showing the rate of gluten-free product prescribing since 1998, where there is a gradual increase until 2011, when guidance changed to recommend only prescribing of staple foods such as bread and flour. Recently there has been a sharper decline.
In our second full year of existence we produced even more exciting outputs and continued to grow. You can see the team on our website: Emma-Jane has been our project manager since the Spring; we have two new part-time coders working for us; and researchers Alex, Nick, Daniel and Karolina all started this year. We’ve delivered a range of great new features on OpenPrescribing, got great progress on numerous pre-launch projects, and have a nice portfolio of papers submitted.
We’ve taken a quick look at the data to see why, despite the number of price concession lines have increased to 91 in November, the estimated total excess cost has reduced. (Reminder - we’ve used September prescribing data to estimate the effects, as that’s the latest data available).
The full table is below, but here are some highlights:
As always, you can find our Drug Tariff viewer at www.openprescribing.net/tariff. We’d love to know what you think about the work we’re doing, or anything to do with the OpenPrescribing tool. Please let us know on Twitter, our Facebook page, or via email at feedback@openprescribing.net.
The PSNC has published the list today of Price Concessions for November 2017. The list is the biggest yet, at 91 lines.
We’ve taken a first stab at calculating the estimated effect for CCGs, using September 2017 prescribing data. The Google Sheet can be found here. (edit) - the Google Sheet now also contains national calculations per presentation and all CCG presentation data.
A couple of calculation changes:
The total for England (actual cost) for November is £38.5m. We’ll do some further calculations when we get the chance. It’s less of an impact than we were expecting - possibly as some of the “big excess” items have been removed. We’ll take another look tomorrow!(edit) - we’ve taken a quick look - and here are some of the reasons why the total cost of price concessions is lower.
We have been writing a lot recently about the effect of price concessions on the NHS primary care drugs bill, and on the problems community pharmacy are facing.
We’ve been asked for some CCG-level data, and so here it is; both for the confirmed data for April-September 2017, and for an estimate for October, which is based on October price concession data with September’s prescribing data.
(edit) We’ve also been asked how the costs were calculated. We calculate the difference in the unit cost, i.e. (price concession cost per pack - DT cost per pack)/pack size and then multiply by the prescription quantity for each affected presentation. Please note that these calculations are based on Net Ingredient Cost (NIC) not Actual Cost, and so the impact to CCGs will be slightly lower (about 7%).
Today we’ve released our new Drug Tariff viewer. It was a dataset that we previously didn’t hold, but thought that it would be useful to turn into a graphical viewer for people to use to see how the reimbursement price on drugs changes over time, and also to use as the basis of the effect that price concessions are having on the NHS.
However, obtaining and normalising the data proved to be a bit of a challenge.
The Drug Tariff, published on behalf of the Department of Health and updated monthly, is a strange and mysterious document, written largely in legalese, and understood by pharmacists and almost no-one else. Ask a GP where they find out the cost of the drug, and they’ll say either their computer system or the BNF. For pharmacists, it’s usually the Drug Tariff (or the Tariff). And that’s usually where the most accurate price will be found.
There has been an interesting and concerning story in The Times today regarding shortages on a number of commonly-used medicines and a corresponding increase in the costs.
Here at OpenPrescribing we have been taking a look at these data as well, and trying to estimate to the cost to the NHS this year.
As the Times article suggested, the excess costs are now hitting £50m per month, with £175m extra spent in primary care by September:
Analyse prescribing without a denominator, explore a new pregabalin measure based on milligrams, and use improved three-month measure breakdowns.
Explore prescribing trends from 1998 to 2016 with the new Long Term Trends tool, alongside an updated pregabalin measure based on prescription items.
We have created a new interactive tool for exploring the national Prescribing Cost Analysis (PCA) data, allowing you to investigate prescribing trends going back to 1998. The PCA data contains annual data on all drugs dispensed in the community in England. Note this makes it slightly different to the monthly dataset used elsewhere on OpenPrescribing which shows how items were prescribed in England. This means that, for example, in PCA data generic products will not appear until the generic is available to be dispensed, and prescriptions written in Wales will be included provided they were dispensed in England.
New measures track NHS England’s low-priority treatments, while drug-level breakdowns help practices and CCGs investigate prescribing variation.
Today we launch another exciting new feature on OpenPrescribing. NHS England recently shared a list of 19 classes of treatment which they think should not be prescribed by GPs. These treatments were advised against on the grounds that they are ineffective, and therefore wasteful, or at least “low priority”.
We think it’s good for everyone to be able to see what GP practices are prescribing: the GPs themselves, but also patients, journalists, commissioners of health services, the public, medicines optimisation teams, and indeed anyone who is interested in exploring and improving healthcare.
Today we launch another new feature on OpenPrescribing. As you will probably know, we have various standard prescribing measures which show how a practice or CCG is prescribing in comparison with their peers. These are presented as percentages or rates, and often the maths is very simple: what is the proportion of “undesirable drug” divided by “all drugs in that class”. But sometimes there are lots of drugs in the “numerator”, the top half of the equation. For these measures, if a practice is doing badly, we wanted it to be easy for everyone to see exactly which drugs are contributing to that score.

At OpenPrescribing, we provide tools for analysing prescribing behaviour in primary care in the NHS in England. If you work with prescribing data, you may have noticed that practices which are “dormant” apparently continue to prescribe. This short article explains why, for the curious.
Our prescribing data comes from the NHS Business Services Authority (NHSBSA), who are responsible for processing dispensing information supplied by pharmacies. Each line of the data includes a practice code which uniquely identifies the GP Practice that issued the prescription. To understand more about each practice (including its contact details, location, and CCG membership), we cross-reference this code with GP Practice data published by NHS Digital. That data contains a column, status, which sometimes contains the value D, for dormant.
Today we are launching something very exciting: a new tool that identifies over £100m in new prescribing cost savings for the NHS. The average practice can save £50,166 a year by using our tool. These are vastly bigger savings than any other current advice such as “always prescribe generically”. You can use the tool right now, online, for free, at our OpenPrescribing.net service: just look for the “experimental measures” link on any CCG or GP practice page. You can also read our preprint paper describing the extent of the NHS savings, and more detail on the technical background, here; and also our detailed FAQ on various technical matters here.

Recently, we’ve been experimenting with integrating the Dictionary of medicines and devices (dm+d) into our prescribing data. dm+d is the standard dictionary for the medicines and devices used across the NHS, and it contains codes and descriptions for these medicines.
There are several benefits to using dm+d; the most useful side-effect is to allow us to show user-friendly names for drugs. The canonical names for drugs in the NHS prescribing data are sometimes very hard to read. They are taken from the NHS’ own version of the British National Formulary, which uses heavily truncated names, full of abbreviations, so they can fit within an arbitrary 15-character limit.
We’ve recently added the option to download your results from the Analyse searches you complete on OpenPrescribing.
There are now three ways to download data from the site. We do also offer free custom extracts, so if there is anything you are struggling to get from the website yourself send us an e-mail.Update: Due to resource limitations we are no longer able to offer free custom extracts.
If you download and use any data from OpenPrescribing please link back to us or cite us.
OpenPrescribing takes open datasets from NHS Digital and NHS Business Services Authority, and makes it easy for people to explore the prescribing dataset. We also use this dataset in our research, and offer bespoke data extracts from the prescribing dataset for researchers, clinicians and NHS staff (get in touch!). In this series of blog posts we’ll explain key concepts and share our knowledge of the prescribing dataset. In the first blog, we take a look at BNF codes.
Today NHS England announced it is reviewing the prescribing of medicines which it deems to be “ineffective, unnecessary [and] inappropriate for prescription on the NHS”.
We make no comment here on whether it is a good or a bad idea for the NHS to stop prescribing these items. We are keen that everyone in the NHS should use data better, to help understand who is prescribing what, and below we show how you can use OpenPrescribing to investigate the prescribing of these items in your area.
We launched our e-mail alerts on OpenPrescribing to help people keep track of prescribing trends at their GP Practice or CCG. Our alerts send you a monthly e-mail highlighting any new signals in our prescribing measures (including the new measures we launched this month!). This will help you keep track of changes in prescribing, as our alerts can help you find changes that might otherwise be difficult to spot by eye.
You can sign up to receive alerts for any GP Practice or CCG in England by going to the dashboards and entering your e-mail address. We will then send you monthly updates tailored for the practice or CCG you are interested in.
We’ve been spending some time at OpenPrescribing designing a set of new measures to identify interesting variations in prescribing behaviour across the country.
We’ve talked to people from CCGs, and have looked (via Freedom of Information requests) at a number of CCG schemes for improving prescribing, and have come up with a number of areas that we think are important.
Some, like the opioids measure, are important for both cost and clinical reasons. Others, such as the glaucoma measure, show where there is prescribing by brand, which we don’t think is necessary. We also have measures, like generic diltiazem, which show where we think there is prescribing which doesn’t meet national guidance on how they should be prescribed.
OpenPrescribing was featured in a recent TARGET antibiotic webinar, which shows how you can use the site to explore antibiotic prescribing in your local CCG or GP practice. It looks at the antibiotic measures featured on our CCG & GP practice dashboards, and how to construct your own queries on the Analyse page.
The webinar demonstrates a range of tools that can be used to take an in depth look at antibiotics - and OpenPrescribing is featured from 5:30. If you want to have a go at using the Analyse page yourself (to look for antibiotics or any other drug!) we’ve written some guidance here.
In our first full year of existence we’ve grown fast, recruiting lots of new staff. You can see us all on our new website: Lydia our project manager started in the Spring, as did Seb, our new coder; Lisa, our community engagement manager, started over the summer; Helen, our new researcher, started in December, with two more researchers starting in January. For our OpenPrescribing work we’ve been joined by Richard as our pharmaceutical advisor. We’ve also been lucky enough to pull in a huge team of excellent students including Jess, Sarah, Mark, and the mighty COMPare project team of Henry, Aaron, Ioan, Philip, and Eirion. We’ve now delivered some of our early projects, and have a nice portfolio of papers submitted already.
How do you know if your product is really working for users? You can guess, you can ask them, or best of all, you can watch them actually using it.
With OpenPrescribing, we want to make it easier for Clinical Commissioning Groups (CCGs) to monitor prescribing behaviour, and for GPs to prescribe in the best way. So it’s important that it really does help those users do those things. And the only way to verify that is with user research.